

At 11 p.m., the kitchen table is covered with unopened mail, a half-finished cup of coffee, and a phone showing another missed call from work. A parent, partner, or sibling is trying to decide whether the household is facing a difficult season or a mental health problem that requires professional care. The person at the center of the concern may look composed in public, yet at home they're sleeping poorly, withdrawing, missing responsibilities, or reacting with anger that wasn't typical before.
Families in this position need three practical answers. They need to understand what the warning signs mean, know what they can do at home tonight, and find a realistic Massachusetts path to professional treatment. They also need a clear reminder that mental health support for families includes the caregiver, not only the person with the diagnosis.
Family members aren't spectators in recovery. They often monitor symptoms, support treatment follow-through, notice changes first, and absorb the pressure of crises. The right same-day outpatient program can provide structure while allowing a loved one to remain connected to home, work, or school when safety permits. The sections below turn concern into specific action, with family-inclusive care at the center.
Table of Contents
- The Moment a Family Decides Something Has to Change
- What Family-Centered Mental Health Support Means
- Recognizing When a Family Member Needs Real Help
- What Families Can Do at Home Starting This Week
- Matching the Right Level of Care to the Situation
- How Cedar Hill Behavioral Health Walks Families Through Care
- Crisis Planning and Communication Templates Families Can Reuse
- Your Family's Next 7 Days and How to Start
The Moment a Family Decides Something Has to Change
The decision for help usually follows a pattern. A spouse sees every conversation become an argument. A parent watches a young adult stop attending class and sleep through the day. An adult child realizes that depression, bipolar symptoms, trauma reactions, OCD, or anxiety now directs the household's choices.
That pattern calls for action, not “wait and see.” Family caregiving for mental health already involves millions of people in the United States. The U.S. Department of Health and Human Services estimated that 13 million people provided unpaid care for an adult family member or friend with mental health problems in 2019. NAMI separately estimates that at least 8.4 million people care for an adult with a mental or emotional health issue, with caregivers spending an average of 32 hours per week on unpaid care (U.S. HHS data on family caregivers).
Three decisions to make this week
- Name the pattern: Record what changed, when it began, and how it affects sleep, relationships, work, school, or safety.
- Change the home response: Use brief, calm check-ins. Repeated confrontations, lectures, and attempts to force insight usually increase resistance.
- Open a care pathway: Contact a treatment center for an assessment before symptoms become an emergency.
Family participation also reflects the history of community mental health care. The 1980 Mental Health Systems Act helped advance broader community mental health services and marked movement away from institution-centered care toward community and family-based support (historical context from U.S. HHS).
Caregivers need support while they coordinate appointments, respond to symptoms, and protect household stability. Treat that strain as clinical information, not a private burden.
Practical rule: Do not wait for a dramatic crisis to justify help. Persistent disruption already gives the family enough information to act.
What Family-Centered Mental Health Support Means
Family-centered mental health support makes the household part of the treatment environment. The individual remains the patient, while the care team also addresses communication, routines, stressors, boundaries, and practical responsibilities that shape recovery at home.
Caregivers are not bystanders waiting for updates. They often notice changes between appointments, manage daily logistics, and absorb the strain of symptoms and setbacks. Treatment should give them clear roles, usable language, and support for their own wellbeing.
The household is part of the treatment plan
The clinician provides direct treatment. Family members help shape the conditions around it, including sleep routines, communication, recovery time, boundaries, and responses to setbacks. They cannot do the work for the patient, but their daily responses can either support treatment or intensify conflict.
Family-inclusive care can involve:
- Shared treatment planning, with the client's consent and clear privacy boundaries.
- Family therapy, where relatives practice communication without criticism, blame, or escalation.
- Psychoeducation, covering symptoms, treatment options, warning signs, and crisis responses.
- Communication routines, including brief check-ins, agreed boundaries, and plans for difficult conversations.
- Caregiver support, addressing anxiety, depression, poor sleep, isolation, and burnout.
Family participation is part of care, not an optional favor. A U.S. Department of Veterans Affairs evidence review found that family-involved psychosocial treatments for adult mental health conditions were, overall, as effective as or more effective than individually oriented psychotherapies, with two exceptions (VA evidence review on family-involved treatment).
Structured, clinician-led support also has stronger backing than informal support alone. A review found that programs combining instruction, information, and advocacy were most effective, while peer-led models had the weakest evidence base. In early psychosis, family interventions improved caregiver distress and burden and reduced harmful expressed-emotion patterns compared with usual care (review of family support programs).
Families can review the Velma cognitive support program for general caregiver-oriented guidance. For sessions and planning that directly include relatives, family therapy at Cedar Hill Behavioral Health offers a relevant treatment option.
Start with one family meeting this week. Agree on who will communicate with the care team, which boundaries apply at home, and how caregivers will get support before exhaustion becomes another household crisis.

Recognizing When a Family Member Needs Real Help
A family member may still attend work or school while struggling severely at home. The right question is whether a persistent pattern is disrupting ordinary life, relationships, or safety.
Behavioral changes
Look for a clear departure from the person's usual behavior:
- Sleep becomes severely disrupted, reversed, or unusually limited.
- The person withdraws from family, friends, school, or work.
- Alcohol or drug use increases, especially as a way to manage distress.
- Work, school, appointments, or household responsibilities begin to slip.
- The person becomes unusually impulsive, agitated, secretive, or risk-seeking.
A functional public image does not rule out serious symptoms. Someone may keep working while spending evenings in panic, refusing meals, checking repeatedly, or remaining unable to sleep.
Emotional signals
Persistent sadness, hopelessness, intense anxiety, panic, irritability, anger outbursts, intrusive thoughts, or emotional numbness require attention. Families should listen for plain statements such as “nothing matters,” “everyone would be better without me,” or “the thoughts won't stop.” These words are meaningful warning signs, even without clinical language.
Functional and safety red flags
Concern becomes urgent when a person cannot reliably manage hygiene, food, medication, transportation, finances, or basic responsibilities. Threats of self-harm, access to lethal means, severe disorganization, dangerous intoxication, or behavior that places another person at immediate risk require crisis intervention, not a routine appointment.
Use a clear threshold:
If symptoms have lasted more than two weeks, are worsening, or are disrupting sleep, work, school, or relationships, arrange a professional assessment.
School refusal, anxiety, and escalating avoidance need coordinated family action. Guidance on when your child refuses school can help caregivers identify the next conversation and decide when outside support is needed. If a loved one refuses or minimizes care, use this guide on how to get someone mental health help to plan a direct, respectful approach.
Caregivers should record changes, agree on who will contact the care team, and decide what would trigger same-day help. In Massachusetts, families can also contact Cedar Hill Behavioral Health to discuss available care and determine the appropriate next step.

What Families Can Do at Home Starting This Week
Home strategies won't replace assessment or treatment. They can reduce friction, improve information available to clinicians, and make the household safer while care is being arranged.
Start with a short daily check-in
Use a predictable time and keep the conversation brief. A parent might say, “There's no pressure to solve everything tonight. What feels hardest today, and what would make the next few hours safer?” A partner could ask, “Would listening, practical help, or quiet company be most useful?”
The purpose is connection, not interrogation. If the loved one says they don't want to talk, the family member can respond, “That's okay. The offer remains open, and a check-in will happen tomorrow.”
Stabilize routine before demanding major change
A consistent wake time, regular meals, medication reminders when appropriate, and reduced evening stimulation can create a more predictable baseline. Families shouldn't turn routine into punishment. The goal is to make the next manageable action obvious, such as taking a shower, eating something simple, or attending one scheduled appointment.
Reduce criticism and emotional overinvolvement
Repeated criticism can intensify defensiveness. Excessive monitoring can also make an adult feel controlled. Families should name the pattern early: “The conversation is becoming heated, so a short break is needed. The issue will be revisited after everyone has cooled down.”
Structured family interventions have been associated with lower caregiver burden and improved illness knowledge. In one brief multifamily program, six sessions over 1.5 months reduced caregiver burden and depression, with caregiver burden improving relative to control at p=0.031. In the active group, depression scores fell from a mean of 14.20 to 6.20, while the control group remained at 14.20 to 14.20 (trial of brief multifamily psychoeducation).
Protect one block of caregiver recovery time
Caregiver self-care needs to be scheduled, not left for the day when everything else is finished. Another trusted adult might cover transportation, meals, supervision, or phone calls so the primary caregiver can sleep, exercise, attend an appointment, or sit in uninterrupted quiet.
Family caregiving can carry a serious psychological burden. APA's summary of caregiving data reports that two in three caregivers experience high emotional stress, nearly half report physical strain, and about one in four feel isolated and alone (APA summary on family caregiver mental health).
Track symptoms without turning the home into a surveillance system
A one-page record can include sleep, appetite, mood, panic, substance use, medication concerns, major triggers, and safety changes. The record should capture observable facts rather than labels. “Slept three hours and missed work” gives a clinician more useful information than “seemed unstable.”

Matching the Right Level of Care to the Situation
Families often choose care based on fear. They assume the only alternatives are doing nothing or entering a hospital. Massachusetts outpatient programs provide a middle path for people who need more structure than weekly therapy but don't require inpatient containment.
Compare the practical options
| Program | Hours per Week | Typical Duration | Best Fit for Families |
|---|---|---|---|
| Partial Hospitalization Program, PHP | Varies by program | Varies by clinical need | Significant symptoms requiring intensive daytime structure while the person returns home when safe |
| Intensive Outpatient Program, IOP | Varies by program | Varies by clinical need | Moderate to significant symptoms needing frequent treatment alongside home, work, or school |
| Standard Outpatient, OP | Varies by provider | Ongoing as clinically appropriate | Stable symptoms managed through regular individual, group, medication, or family sessions |
| Family therapy | Varies by treatment plan | Short-term or ongoing | Conflict, caregiver strain, communication problems, boundary setting, and shared relapse planning |
| EMDR | Varies by clinician and treatment plan | Varies by trauma history and response | Trauma-driven symptoms when a qualified clinician determines trauma processing is appropriate |
| Medication management | Appointment schedule varies | Ongoing review as needed | Mood, anxiety, sleep, or other symptoms requiring medication assessment and monitoring |
PHP and IOP are especially useful when symptoms are interfering with ordinary functioning but the person can remain safely connected to home. They provide clinical structure during the day, while family members can participate in real-life planning rather than waiting for restricted visiting periods.
Medication is one tool, not the entire plan
Medication management can help stabilize mood or reduce symptom intensity, but it doesn't teach communication, rebuild trust, establish boundaries, or help caregivers respond to warning signs. A thoughtful plan may combine medication with individual therapy, group treatment, family sessions, skills training, and routine support.
EMDR can be appropriate when trauma is driving intrusive memories, avoidance, hyperarousal, or related symptoms. It should be considered within a full assessment, not selected as a universal solution for every diagnosis.
Families should ask four questions before choosing a level of care:
- Can the person remain safe at home?
- How much structure is needed between appointments?
- Can the family participate without taking control away from the client?
- Does the program offer a step-up or step-down option if symptoms change?
The best match is the least disruptive level that still provides enough clinical support. If safety is uncertain, the family should use crisis resources rather than relying on an outpatient schedule.
How Cedar Hill Behavioral Health Walks Families Through Care
For Massachusetts families who need a concrete starting point, Cedar Hill Behavioral Health provides same-day admissions and a full outpatient continuum in Southborough. The center is located at 120 Turnpike Rd., Suite 120, Southborough, MA, and offers PHP, IOP, and OP services so treatment intensity can align with symptom severity and change over time.
Begin with an assessment, not a perfect explanation
A family doesn't need to arrive with a diagnosis or a polished account of every symptom. The admissions conversation can identify what changed, how the household is coping, whether safety concerns exist, and which level of care may fit.
Cedar Hill's process includes same-day assessment, instant insurance benefits verification, and payment plans for self-pay clients. Free confidential tools, including an online depression test and an adult ADHD self-screen, can offer a low-friction way to organize concerns before speaking with a clinician. These tools don't replace an evaluation, but they can help a person describe what they're experiencing.
Keep the family involved while preserving autonomy
Treatment may combine individual, group, and family therapy with cognitive behavioral therapy, mindfulness, medication management, and trauma-focused services such as EMDR when clinically appropriate. Family members can contribute observations, learn communication and boundary-setting skills, and participate in crisis planning while the client's privacy and independence remain central.
Cedar Hill is veteran-owned and provides veteran services, which can matter when military culture, deployment experiences, or transition-related stress affect how a veteran or family member approaches care. Licensed mental health and medical professionals support treatment for concerns including anxiety disorders, depression, bipolar disorder, borderline personality disorder, OCD, PTSD, and other mood disorders.
The next step is simple. A family member can call (508) 310-4580 and request a same-day call back. The admissions team can explain available care, verify benefits, and help determine whether PHP, IOP, OP, family therapy, medication management, or another service fits the situation.
Crisis Planning and Communication Templates Families Can Reuse
A crisis plan should be written before the next crisis. Keep it accessible to the household and update it when medications, providers, addresses, or emergency contacts change.
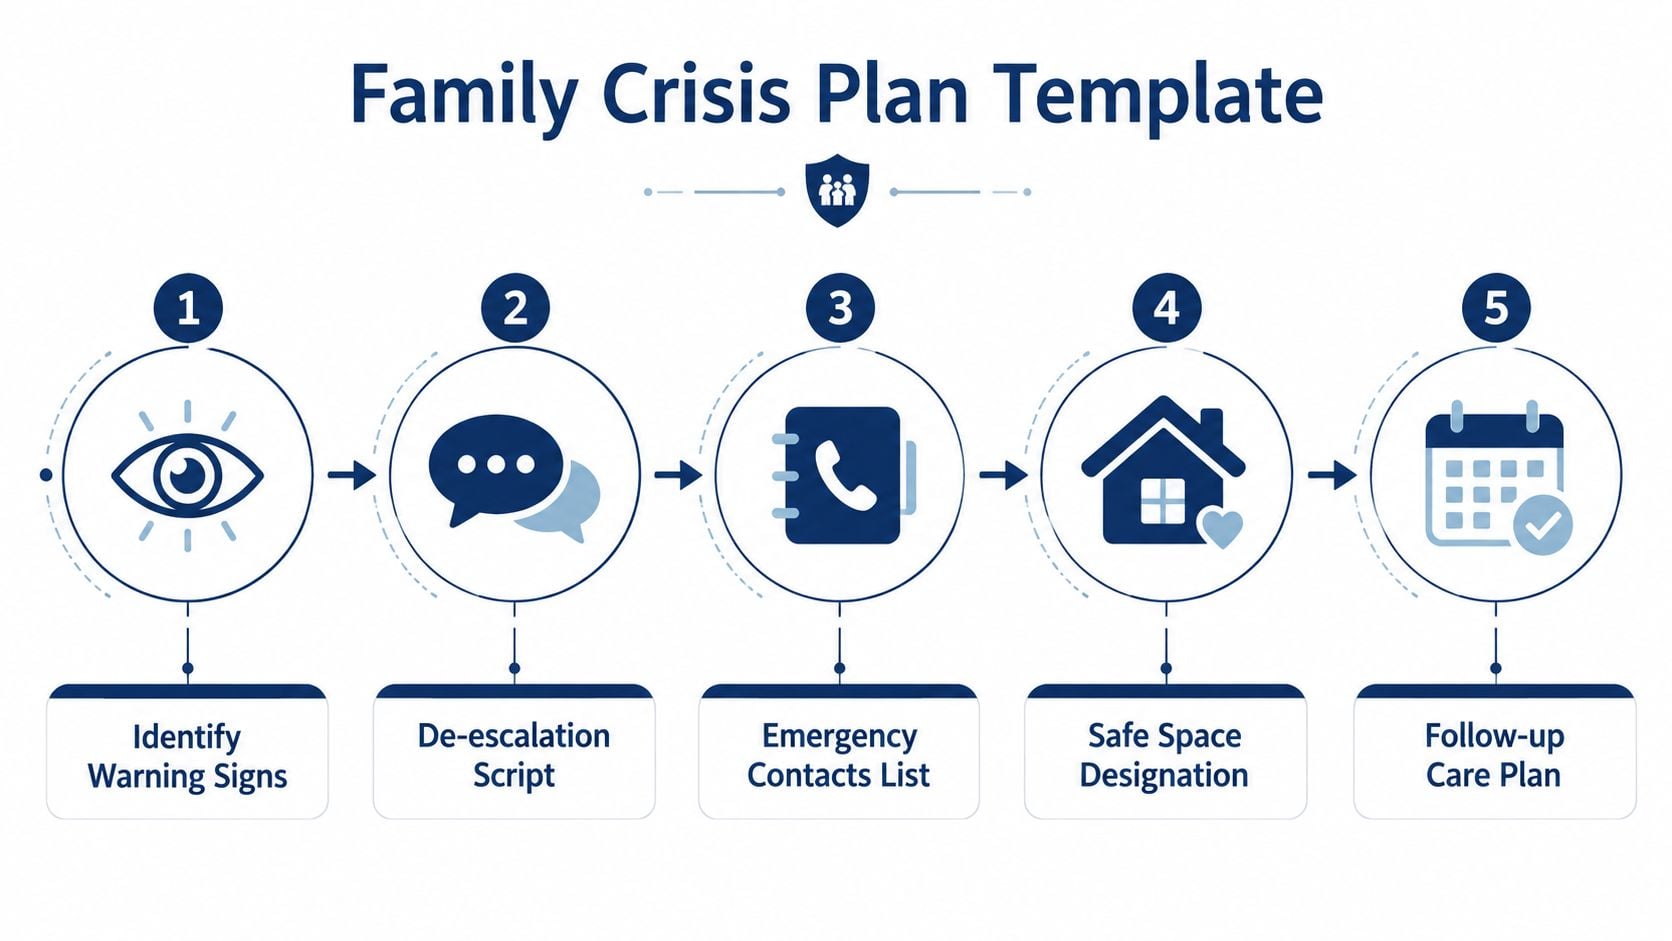
Build the plan around five decisions
- Identify warning signs: Record the changes that usually appear before escalation, such as severe insomnia, isolation, intoxication, hopeless statements, or agitation.
- Choose a de-escalation script: Decide who speaks, what tone to use, and which phrases should be avoided.
- List emergency contacts: Include the treatment team, trusted relatives, the nearest emergency department, and crisis resources.
- Designate a safer space: Identify where people can separate, reduce stimulation, and remove access to dangerous items when possible.
- Set follow-up steps: Write down who contacts the clinician, who stays with the person, and what happens after the immediate danger passes.
Call 988 for the Suicide and Crisis Lifeline when someone is experiencing suicidal thoughts, severe emotional distress, or a mental health crisis requiring immediate support. Call 911 when there's an immediate threat to life or physical safety, a weapon is involved, severe medical impairment is present, or emergency responders are needed. Families should plainly describe the mental health crisis, known diagnoses, medications, threats, substances, access to weapons, and immediate safety risks.
Useful communication templates include:
- Observation opener: “A change has been noticed in sleep, mood, and daily responsibilities. The concern isn't blame. A professional assessment is needed, and support is available.”
- Treatment invitation: “Treatment doesn't require solving everything today. An assessment can clarify what's happening and what level of support would help.”
- Boundary statement: “The household won't continue conversations involving threats or insults. The conversation can resume when everyone is safe, or with a clinician present.”
Caregivers also need a self-check. Persistent anxiety, depression, sleep disruption, isolation, hopelessness, or inability to perform basic responsibilities signals that the caregiver needs professional support, not more endurance. The 988 mental health resource can help families organize crisis information and identify immediate next steps.
Your Family's Next 7 Days and How to Start
A family doesn't need to fix the entire situation in one conversation. The goal for the next week is to create clarity, reduce avoidable conflict, and connect with qualified care.
- Day 1: Name the situation without shame. Write down the changes affecting mood, behavior, functioning, relationships, and safety.
- Day 2: Start one home strategy, such as a brief daily check-in or a consistent wake time. Don't introduce every rule at once.
- Day 3: Map warning signs and triggers. Note what tends to precede escalation and what helps the person settle.
- Day 4: Call (508) 310-4580 to request a same-day assessment at Cedar Hill Behavioral Health in Southborough.
- Day 5: Prepare a one-page family summary with symptoms, timeline, medications, prior treatment, safety concerns, and the family's main questions.
- Day 6: Set one caregiver boundary. Arrange respite, decline one nonessential obligation, or schedule the caregiver's own clinical appointment.
- Day 7: Schedule the first follow-up and reassess the plan. Keep what works, remove what creates conflict, and share meaningful observations with the treatment team.
Families aren't rescuing a loved one by taking these steps. They're building the household conditions that make recovery more possible while respecting the person's autonomy. The right treatment team will treat relatives as informed partners, teach practical skills, and address caregiver wellbeing as part of the clinical picture.
Cedar Hill Behavioral Health offers family-inclusive PHP, IOP, and OP treatment in Southborough, Massachusetts, with same-day assessment, benefits verification, therapy, medication management, and EMDR access when appropriate. Families can visit Cedar Hill Behavioral Health or call (508) 310-4580 to begin an admissions conversation and request prompt guidance.








