

At dinner, a friend suddenly goes quiet, grips the edge of the table, and excuses themselves for the third time in a week. Later, they apologize for being difficult, while the people around them wonder whether to offer reassurance, insist they stay, or rearrange everything to prevent another episode. That uncertainty is painful, but how to help someone with anxiety becomes clearer when support includes compassion, structure, boundaries, and a plan for professional care.
Anxiety disorders are widespread. The World Health Organization's mental health data estimates that anxiety disorders affected 359 million people worldwide in 2021 and that about 4.4% of the global population currently experiences an anxiety disorder. A caregiver can't treat anxiety alone, but a caregiver can recognize warning signs, respond without reinforcing avoidance, and help the person reach the right level of treatment.
Table of Contents
- Recognizing Anxiety Signs in Someone You Care About
- Immediate Support Strategies During Anxiety Episodes
- What Helps Versus What Makes Anxiety Worse
- Evidence-Based Treatments That Work for Anxiety
- Setting Boundaries and Protecting Your Own Mental Health
- When and How to Seek Professional Help in Massachusetts
Recognizing Anxiety Signs in Someone You Care About
Dinner plans rarely reveal the whole story. The person who leaves early may have spent the day rehearsing conversations, worrying about an undisclosed mistake, or bracing for a physical sensation they fear will become a panic attack. Anxiety often appears first as a pattern of changed behavior, not as a clear statement such as “I'm having an anxiety disorder.”
Everyday stress usually eases when the immediate pressure passes. Clinical anxiety keeps interfering with ordinary life. A person may withdraw from social plans, become unusually irritable when routines change, sleep poorly, or complain of headaches, stomach problems, dizziness, or exhaustion. The person may not connect those experiences to anxiety, or may hide them because they feel embarrassed.

Four patterns caregivers commonly see
Generalized worry loops involve persistent concern about health, money, work, relationships, safety, or ordinary decisions. The subject changes, but the mental process stays active. Reassurance may help briefly before a new question takes its place.
Panic episodes arrive as sudden surges of intense fear. The National Institute of Mental Health description of panic attacks includes symptoms such as a racing heart, shortness of breath or choking sensations, sweating or chills, weakness or dizziness, trembling, and a feeling of impending doom. During an episode, the person may believe something medically catastrophic is happening.
Social avoidance can look like skipped events, canceled appointments, silence in groups, refusal to make phone calls, or dependence on a trusted person to speak for them. The fear often centers on judgment, embarrassment, or visible anxiety.
Obsessive-compulsive cycles pair intrusive thoughts, images, or urges with repetitive behaviors or mental rituals intended to reduce distress. Repeated checking, cleaning, questioning, researching, or asking others to confirm safety can become part of the cycle.
A practical observation check
Caregivers don't need to diagnose. They need to notice whether anxiety is becoming persistent and disabling:
- Frequency: Does the pattern return repeatedly rather than appearing around one isolated stressor?
- Intensity: Does fear seem far greater than the situation calls for?
- Duration: Has the change continued instead of resolving as circumstances improve?
- Functional impairment: Is the person struggling with work, school, sleep, relationships, hygiene, travel, or daily responsibilities?
Practical rule: Notice the pattern without turning the person into a problem to solve.
Early recognition gives a supporter time to raise the subject gently, document changes, and encourage an assessment. Readers looking for a clearer symptom overview can review anxiety symptoms and warning signs before starting that conversation. The supporter becomes an important first responder in the mental health chain, not by acting as a therapist, but by helping the person move from confusion toward care.
Immediate Support Strategies During Anxiety Episodes
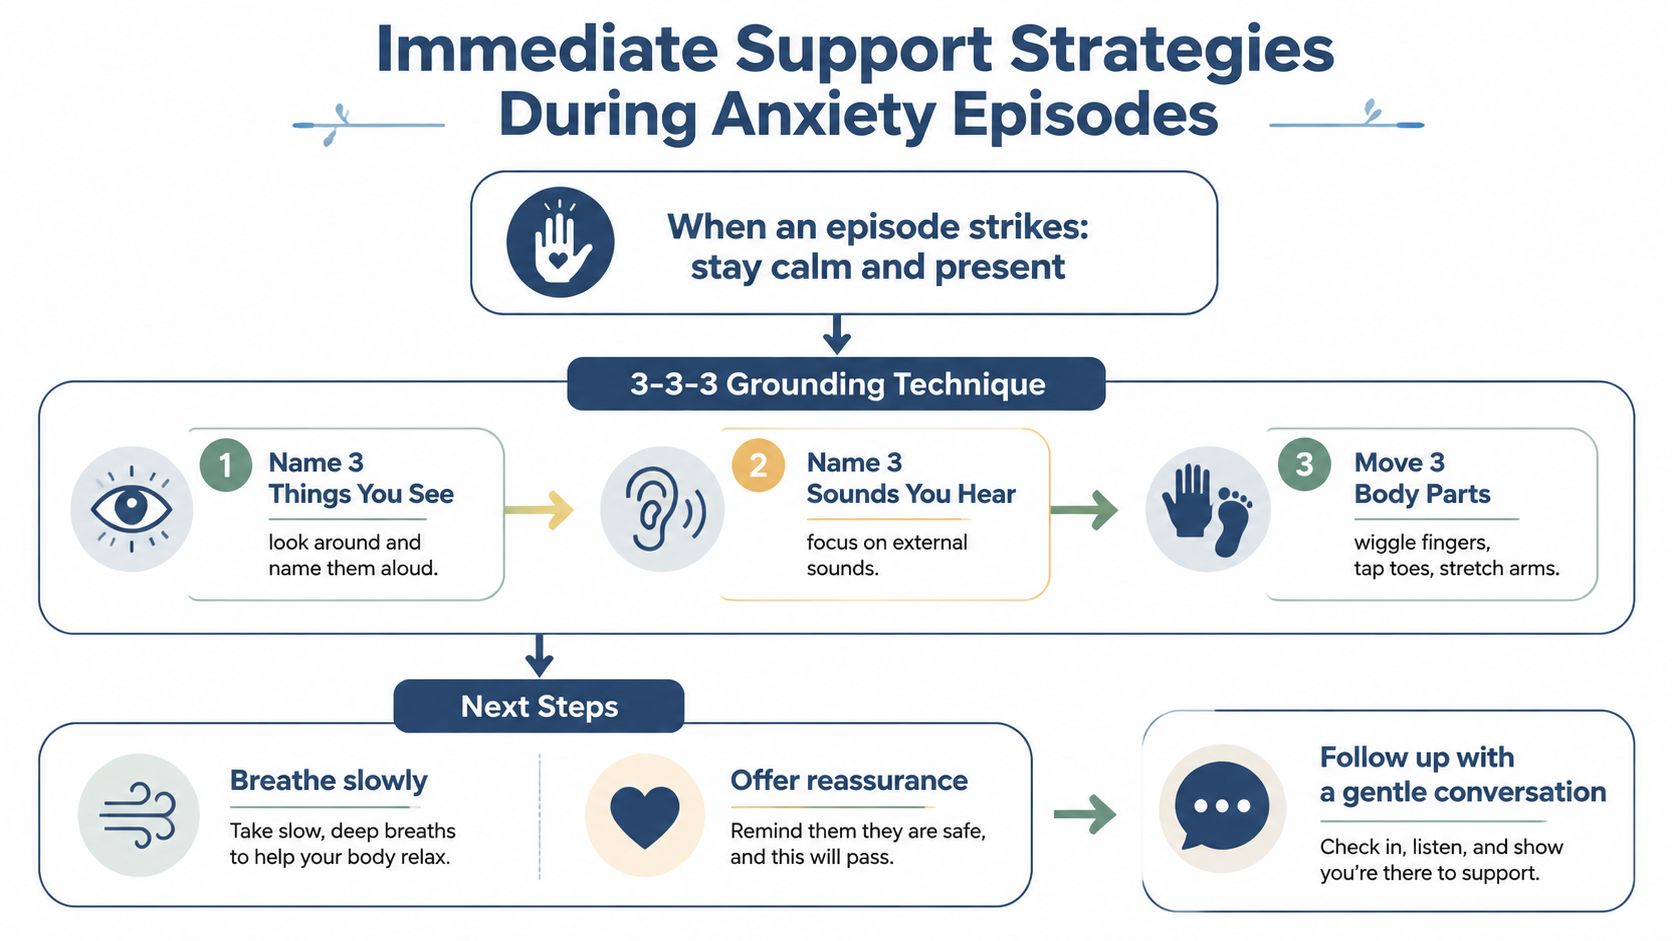
An acute episode requires a calm presence, not a debate. The supporter should lower the emotional temperature, orient the person to the present, and ask what kind of contact feels tolerable. A loud voice, crowded room, rapid questioning, or unwanted touch can intensify distress.
Start with the 3-3-3 grounding technique:
- Ask the person to name three things they can see. Encourage them to look around and describe ordinary details, such as a chair, a window, or a blue cup.
- Ask them to identify three sounds they can hear. These might include a fan, traffic, footsteps, or their supporter's voice.
- Ask them to move three body parts. They might wiggle their fingers, tap their toes, rotate their shoulders, or stretch their arms.
Use a steady voice and simple breathing cues
If the person can follow directions, guide box breathing. The supporter can say:
- “Breathe in for four.”
- “Hold for four.”
- “Breathe out for four.”
- “Hold for four.”
Repeat the cycle without demanding perfect timing. Slow diaphragmatic breathing can support the parasympathetic nervous system and help interrupt the body's fight-or-flight response. The objective isn't to force calm. It's to give the body a slower rhythm while the fear response loses momentum.
Say, “I'm right here, you're safe, this will pass.” Keep the words short and repeat them only when they help. Avoid “Calm down,” “It's not a big deal,” “You're overreacting,” or “There's nothing to worry about.” Those phrases dismiss the experience and can make the person feel ashamed.
For additional ideas that can be practiced before a crisis, the guide to instant anxiety grounding methods offers a useful collection of present-focused exercises. A supporter can also learn progressive muscle relaxation as a separate skill, provided the anxious person is comfortable trying it.
Adjust the surroundings, then allow recovery
Reduce noise, harsh light, crowding, and unnecessary conversation. Offer water, but don't insist. Ask whether the person wants physical space, someone sitting nearby, an open door, or a quiet room. Their preference matters, especially if touch or closeness feels overwhelming.
A realistic timeline helps prevent premature pressure:
- First 90 seconds: Stay present, reduce stimulation, and use brief grounding prompts.
- Next five minutes: Continue slow breathing or sensory orientation. Don't demand an explanation or a decision.
- Recovery window: Allow quiet and rest. Later, ask what helped, what made things worse, and whether a professional follow-up is needed.
If symptoms suggest a medical emergency, severe physical illness, intoxication, or immediate danger, emergency medical help takes priority over grounding exercises.
What Helps Versus What Makes Anxiety Worse
Reassurance can feel loving because it brings quick relief. Repeated reassurance, however, can become a ritual. The person asks whether the door is locked, a symptom is dangerous, or someone is angry. The caregiver answers, anxiety falls briefly, and the question returns. Over time, this pattern teaches the brain to seek certainty from another person.
The same cycle grows when supporters speak for the person, cancel every difficult plan, remove every trigger, or take over tasks the person could complete with coaching. These choices reduce distress in the moment but strengthen avoidance. Caregivers should support gradual practice and use structured support for stopping negative thoughts to help the person identify catastrophic predictions and examine them more carefully. The resource can provide useful language, but it does not replace therapy.
Supportive accountability in practice
Validate the emotion without confirming the feared conclusion. “That feels frightening” acknowledges distress. “Yes, this proves something terrible will happen” strengthens the anxiety story.
| Common Instinct, Accommodation | Evidence-Based Alternative, Supportive Accountability |
|---|---|
| “Let me handle that for you.” | “The task feels hard. Take the next manageable step while I stay nearby.” |
| Repeatedly answering the same safety question. | Give one clear answer, then redirect toward coping or the agreed treatment plan. |
| Canceling every activity that triggers fear. | Encourage a gradual, planned approach instead of an abrupt escape. |
| Speaking for the person in social or medical situations. | Help prepare what they want to say, then let them speak when possible. |
| Promising that anxiety won't return. | Acknowledge that discomfort may occur and emphasize that it can be handled. |
Caregivers need a stopping rule. Answer a repeated reassurance question once, offer one coping prompt, and avoid restarting the debate. If the person cannot complete a planned step, scale it down rather than removing it entirely. If avoidance keeps expanding, daily functioning declines, or support requests overwhelm the household, bring the pattern to a qualified clinician.
The shift can feel harsh to someone who equates help with fixing. Staying close while refusing to feed avoidance is compassionate. It gives the person room to tolerate uncertainty and act according to values rather than fear.
Supportive accountability: “The fear is real, and avoidance isn't the only available response.”
Evidence-Based Treatments That Work for Anxiety
Start with cognitive behavioral therapy, the first treatment caregivers should discuss with a qualified clinician. CBT helps a person identify anxious predictions, test the evidence behind them, change behaviors that keep fear going, and approach feared situations gradually. Exposure and behavioral experiments matter because escaping too soon prevents someone from learning what happens.
Research supports structured CBT over indefinite reassurance. A review of randomized clinical trials found better outcomes than control conditions within 12 months after treatment ended. A separate analysis of 65 studies involving 5,048 participants also found CBT more effective than treatment as usual, with benefits that remained among the stronger long-term options after studies with a high risk of bias were removed. The practical recommendation is clear: help the person connect with qualified treatment, then support attendance and practice without becoming the treatment yourself.
Match format and intensity to the person
Computerized CBT can help people who have difficulty attending appointments. A meta-analysis of computerized CBT for DSM-5 anxiety disorders found significantly better results than wait-list care, with SMD 0.92, 95% CI 0.83 to 1.02, across 31 comparisons, P<.001. Format still matters. Research on generalized anxiety disorder found individual CBT more effective than remote CBT, treatment as usual, and wait-list care, while remote CBT did not outperform treatment as usual or wait-list care for anxiety symptoms.
Other therapies may suit particular needs. Mindfulness-based stress reduction develops attention and body awareness without automatically following anxious thoughts. Acceptance and Commitment Therapy helps a person make room for difficult internal experiences while acting according to personal values. Medication management may include SSRIs or SNRIs. Benzodiazepines require careful medical oversight and are generally considered for short-term use because of dependence concerns. Trauma-related anxiety may require trauma-focused care, including EMDR, when a qualified clinician determines that it fits.
Caregivers should help match treatment intensity to functioning, risk, access, and the person's ability to participate.
| Severity Level | Recommended Treatments | Typical Setting | Expected Timeline |
|---|---|---|---|
| Mild, manageable symptoms | Education, skills practice, CBT-informed self-help, therapy consultation | Self-guided support or outpatient care | Progress develops through regular practice and follow-up |
| Persistent symptoms affecting routines | Individual CBT, medication evaluation, mindfulness or ACT skills | Weekly outpatient therapy | The clinician reviews progress and adjusts the plan |
| Symptoms disrupting work, school, sleep, or relationships | More frequent therapy, medication management, group and family work | Intensive outpatient care | The team monitors response and functioning closely |
| Severe symptoms or inability to remain safe and functional | Coordinated psychiatric and medical treatment | Partial hospitalization or inpatient care when necessary | The level of care changes as safety and stability improve |
Choose a plan that includes measurable follow-up rather than passive monitoring. Combined therapy, skills training, family involvement, and medication management may be appropriate when one approach does not provide enough support. The caregiver's role is to help arrange care, notice changes in functioning or safety, and encourage follow-through. A clinician should decide diagnosis, medication, and level of care.
Setting Boundaries and Protecting Your Own Mental Health
A caregiver who stays available every hour of every day eventually becomes exhausted, resentful, or frightened of setting limits. That exhaustion changes the relationship. The supporter may begin answering every reassurance request, avoiding personal plans, or monitoring the anxious person constantly. Those actions can create dependence while leaving the caregiver with no room to recover.
The caregiver's mental load deserves direct attention. Across 47 low- and middle-income countries, caregiving was associated with higher odds of anxiety symptoms, with OR 1.52 and 95% CI 1.40 to 1.65, as reported in a systematic review of caregiver support and anxiety. The same review identified limited evidence for interventions designed specifically for carers of a person with anxiety symptomology. That gap makes structured education and boundaries especially important.

Boundaries that preserve connection
A boundary should describe what the supporter will do, not threaten what the anxious person will lose. Useful scripts include:
- "The supporter can talk about this for fifteen minutes, then needs to return to work."
- "One answer has already been given. The supporter will stay nearby while the person practices the coping plan."
- "The supporter can drive to the appointment, but can't answer every question for the person."
- "The supporter cares and will check in after dinner, rather than staying on the phone all night."
A caregiver should watch for irritability, disrupted sleep, social withdrawal, dread, and resentment. These signs don't mean the supporter loves the person less. They indicate that the current arrangement is unsustainable.
Recovery is part of the care plan
Scheduled time away, personal therapy, peer education, and a family support group can help caregivers make decisions without panic. The updated review of caregiver interventions describes education, training, and information as the strongest evidence category for carer effectiveness, while also noting uncertainty around many common caregiver programs. Peer support and skills-building deserve more attention than generic advice to “be supportive.”
Protecting mental health isn't selfish. It reduces the chance that support turns into surveillance, resentment, or accommodation. A rested caregiver can tolerate discomfort, maintain consistent expectations, and help the anxious person engage with treatment.
When and How to Seek Professional Help in Massachusetts
Informal support has limits. Professional help becomes the right next step when anxiety repeatedly causes panic, disrupts work or school, drives serious avoidance, leads to substance use as a coping method, or produces persistent physical problems such as insomnia and major changes in eating or weight. Suicidal thoughts, self-harm, immediate danger, chest pain, severe breathing difficulty, or confusion require urgent evaluation rather than a routine appointment.

Choose the level of care
Outpatient therapy suits a person who can remain reasonably safe and manage essential daily responsibilities while attending regular sessions. Intensive outpatient programs provide more frequent structured treatment while allowing the person to live at home. Partial hospitalization programs offer a higher level of daytime support for symptoms that require close monitoring and coordinated care. Inpatient treatment is reserved for situations requiring continuous safety supervision or intensive medical and psychiatric stabilization.
The caregiver should ask a clinician to assess symptom severity, safety, functioning, substance use, medical concerns, and the person's ability to participate in treatment. A higher level isn't a punishment. It's a practical response when weekly support can't contain the problem.
Start the conversation without forcing it
Motivational interviewing principles reduce defensiveness. Ask permission before offering advice. Use observations instead of labels: “The person has stopped attending work and is sleeping poorly.” Ask what the person wants to change, reflect their concerns, and offer choices. A caregiver might say, “Would the person be willing to speak with a therapist, a primary care clinician, or an admissions coordinator? The supporter can help with the first call, but the person should decide what feels acceptable.”
Cedar Hill Behavioral Health in Southborough offers same-day admissions, individualized treatment, and PHP, IOP, and outpatient programs for adults who need different levels of support. The center provides therapy, family involvement, evidence-based modalities, medication management, benefits verification, and payment plans for self-pay clients, while accepting most major insurance plans. A caregiver can ask about the assessment process, available programs, coverage, and whether the current symptoms fit outpatient, IOP, or PHP care.
Barriers such as cost, stigma, and scheduling can delay treatment. Request a benefits check, ask about payment options, keep a symptom summary ready, and contact more than one appropriate local service if availability is limited. If there's immediate danger, call 911 or go to an emergency department.
Cedar Hill Behavioral Health offers individualized anxiety treatment through outpatient, IOP, and PHP care, with therapy, family support, mindfulness, CBT, and medication management matched to the person's needs. Families in Massachusetts can visit Cedar Hill Behavioral Health or call (508) 310-4580 to request prompt guidance about assessment and admissions.








