

A partial hospitalization program (PHP) is a structured, high-intensity outpatient mental health treatment providing at least 20 hours of therapy per week for people who need more support than standard therapy but don't require 24-hour inpatient hospitalization. Patients receive concentrated care during the day and return home rather than staying overnight.
A Massachusetts family may recognize the situation immediately. A young adult's depression has deepened, suicidal thoughts have appeared, and getting through work or school has become difficult. The symptoms don't seem urgent enough for an emergency room visit, yet one weekly therapy appointment isn't enough to interrupt the decline. Everyone is left in the frightening space between “not sick enough” for inpatient care and “too unstable” for ordinary outpatient treatment.
PHP was designed for that middle ground. It provides a reliable clinical schedule, daily contact with trained professionals, medication support when appropriate, and time to practice coping skills while the patient remains connected to home and community. The person doesn't sleep at the facility, but the treatment is far more intensive than a standard office visit.
Table of Contents
- Understanding What a Partial Hospitalization Program Really Is
- How PHP Works and What a Typical Day Looks Like
- PHP vs IOP vs Inpatient vs Outpatient Care
- Who Benefits Most from Partial Hospitalization
- Getting Started at Cedar Hill Behavioral Health
- Common Questions About PHP Treatment
- Take the Next Step Toward Structured Mental Health Support
Understanding What a Partial Hospitalization Program Really Is
A structured middle level of care
A partial hospitalization program is a high-intensity outpatient level of care for someone with a serious mental disorder who needs active treatment but doesn't require inpatient containment. Medicare describes PHP as an intensive, structured alternative to inpatient psychiatric hospitalization, generally delivered through a per diem outpatient framework. CMS requires PHP services to provide a minimum of 20 therapeutic hours per week, and federal guidance clarifies that this threshold is an eligibility standard rather than a requirement that every week be billed in an identical way. CMS outpatient payment guidance and Medicare's partial hospitalization coverage information explain how the benefit fits within outpatient care.
A common clinical schedule spreads those hours across several weekdays, often through sessions lasting much of the day. Patients attend group therapy, individual sessions, psychiatric appointments, skills training, and care coordination, then return home in the evening. The home setting matters because clinicians can help patients apply new strategies to actual family, work, school, and community situations instead of practicing only inside a hospital.
Practical rule: PHP is appropriate when a person can remain safe outside a hospital with a dependable plan and support, but still needs treatment throughout much of the day.
Why PHP isn't “inpatient-lite”
PHP isn't a watered-down hospitalization. It has a different purpose and requires a different safety profile. Inpatient treatment provides continuous containment for people facing immediate safety risks, severe medical instability, or symptoms that cannot be managed outside a hospital. PHP focuses on stabilization, structured therapy, and supervised skill development for people who can sleep at home safely.
The model has deep roots in community psychiatry. The concept existed before the 1950s, became more established in the United States after the Community Mental Health Act of 1963, and expanded through Medicare payment policy in the Omnibus Budget Reconciliation Acts of 1987 and 1990. The number of community mental health center-based PHPs grew from 296 in 1993 to 769 in 1997, and by 2016, PHP services were offered by 38.7% of metropolitan hospitals and 11.4% of nonmetropolitan hospitals in the United States. This historical review of PHP development documents that progression.
Families seeking a plain-language overview can also consult the Addiction Resource Center LLC PHP guide, which provides additional context about how day treatment differs from inpatient and routine outpatient care.
How PHP Works and What a Typical Day Looks Like
PHP works because the day has enough structure to create therapeutic momentum. CMS and Medicare guidance identify 20 hours of treatment per week as the minimum standard for this level of care, while Medicare describes PHP as typically involving four to eight hours of care per day. Medicare's outpatient PHP explanation gives families a useful framework for understanding why a PHP day feels closer to a treatment workday than to a weekly appointment.
A representative schedule may look like this:
- Morning arrival and check-in: Staff review mood, sleep, safety concerns, medication changes, and immediate needs. Vitals may be checked when clinically appropriate.
- Skills-focused group: A therapist may lead work on distress tolerance, emotional regulation, cognitive restructuring, or communication.
- Individual therapy or medication management: The patient meets privately with a therapist, psychiatric clinician, or prescriber to address personal symptoms and treatment decisions.
- Lunch and peer connection: A planned break provides time to eat, decompress, and experience supportive contact with other participants.
- Specialized afternoon group: The topic may involve DBT skills, trauma-focused work, psychoeducation, relapse prevention, or family relationships.
- Closing review: The patient identifies warning signs, coping tools, and a safety plan for the evening at home.
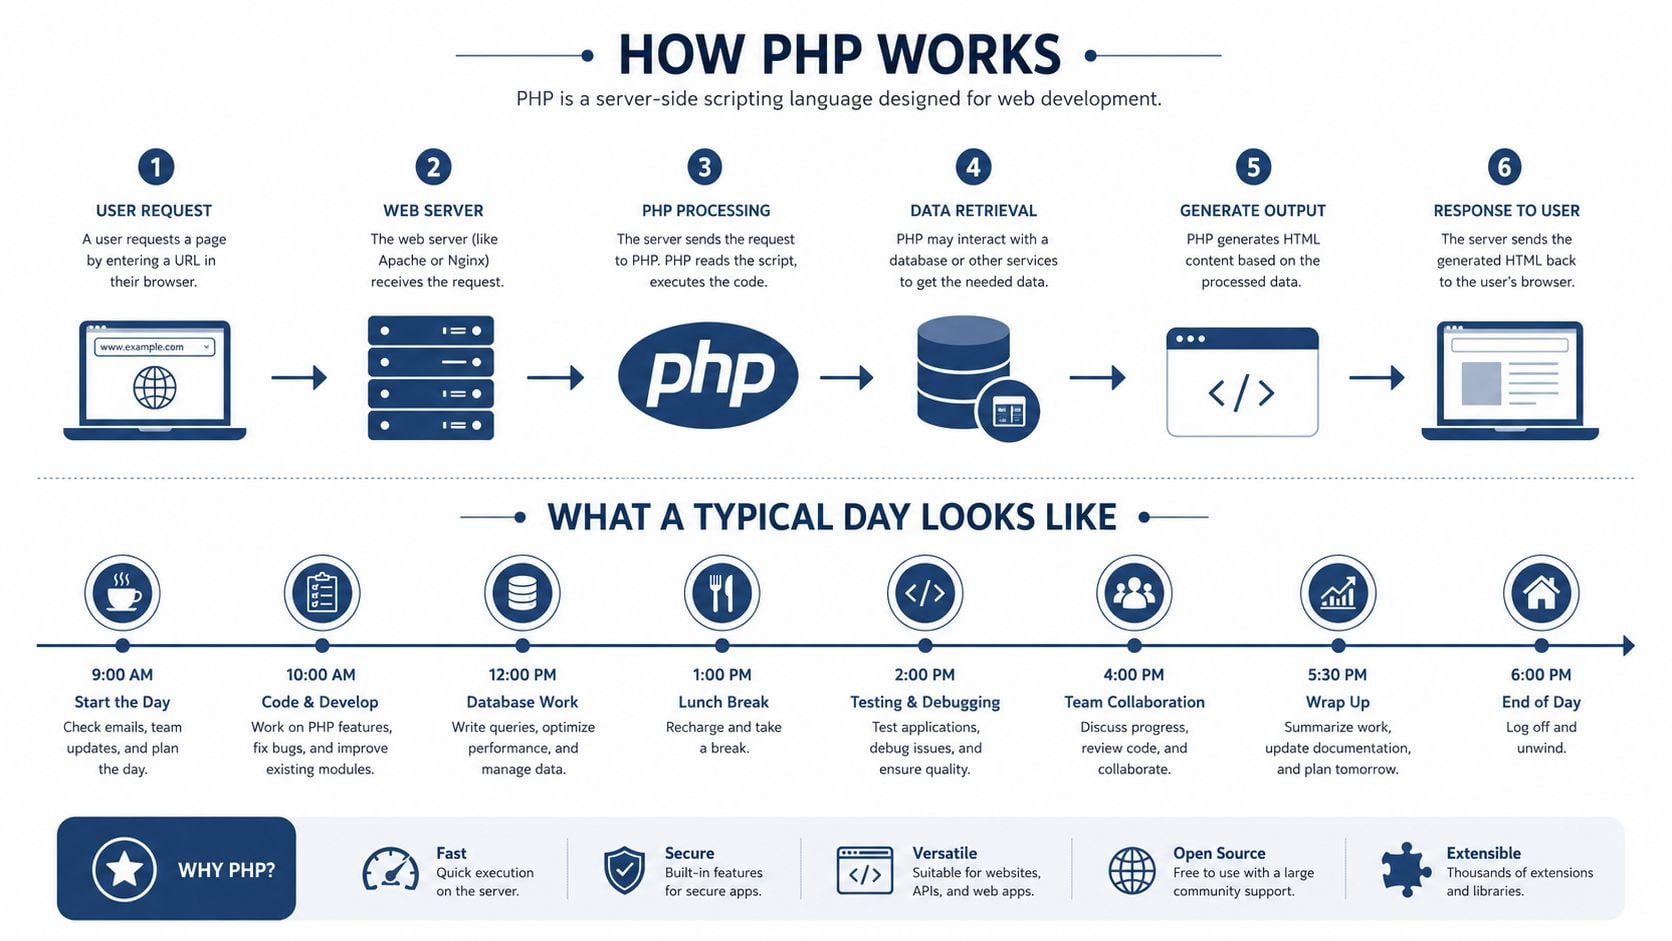
Programs often operate during weekday daytime hours, although schedules vary by provider and some programs offer evening options. The exact mix of services depends on the patient's diagnosis, safety needs, treatment goals, and medication plan. A person may receive CBT-based work for depressive thinking, DBT exercises for intense emotions, trauma-informed care, family sessions, and psychiatric monitoring within the same treatment plan.
Attendance isn't passive. Patients are expected to arrive consistently, participate in groups, communicate openly about safety, and practice skills between sessions. Assignments may include tracking mood, challenging an automatic thought, using a grounding exercise, or preparing a conversation with a family member.
That daily repetition helps clinicians see what works and what doesn't. Standardized measures such as PHQ-9 and GAD-7 are increasingly used to track depression and anxiety symptoms over time, supporting more measurable decisions about continuing, changing, or reducing treatment intensity. Recent outcomes-focused PHP research discusses this movement toward measurement-based higher-intensity outpatient care.
PHP vs IOP vs Inpatient vs Outpatient Care
The right level of care depends on safety, symptom severity, daily functioning, available support, and the amount of clinical contact needed. A person can move between levels as symptoms change. Someone may step down from inpatient treatment into PHP, then into IOP and routine outpatient care, while another person may enter PHP directly from the community after weekly therapy stops being sufficient.
| Feature | Inpatient | PHP | IOP | Outpatient |
|---|---|---|---|---|
| Treatment intensity | Continuous hospital-based care | Intensive daytime treatment with at least 20 therapeutic hours weekly | Fewer structured hours than PHP | Periodic therapy or medication appointments |
| Living arrangement | Patient stays in the hospital | Patient sleeps at home | Patient sleeps at home | Patient lives at home |
| Appropriate severity | Immediate safety risk, severe instability, or need for constant monitoring | Serious symptoms requiring daily structure without 24-hour containment | Symptoms needing regular support but more flexibility | Symptoms manageable with periodic clinical contact |
| Typical duration | Determined by safety and stabilization needs | Determined by progress and clinical necessity | Often used as a step-down or maintenance level | Ongoing as clinically appropriate |
| Insurance expectations | Coverage depends on medical necessity and plan rules | Coverage depends on medical necessity, authorization, and plan rules | Coverage varies by plan and clinical documentation | Coverage varies by plan and service |
IOP is less intensive than PHP and may suit someone who can manage more of the day independently but still needs recurring group and individual treatment. Standard outpatient care offers the greatest flexibility, but it may not provide enough contact during an acute deterioration. Readers comparing PHP with IOP can review Cedar Hill's explanation of intensive outpatient therapy.
A useful distinction: The question isn't only whether someone has a diagnosis. The question is how much structure is needed to keep treatment active and daily life safe.
Choosing too little support can leave a person cycling through worsening symptoms without enough intervention. Choosing inpatient care when 24-hour containment isn't necessary can disrupt work, school, family routines, and community connection. A clinical assessment helps determine whether the person needs a step up, a step down, or a different form of care altogether.
Who Benefits Most from Partial Hospitalization
PHP can fit adults with significant depression, generalized anxiety, PTSD, bipolar disorder, emotional dysregulation, or co-occurring substance use concerns when they can participate safely outside a hospital. The treatment team looks beyond the diagnosis. They consider suicidal thinking, self-care, sleep, medication response, substance use, family support, housing stability, and the person's ability to follow a safety plan.
Evidence supports PHP as a meaningful option for selected adult populations. A systematic review found no differential outcome between partial hospitalization and full hospitalization across psychopathology, social functioning, family burden, or service use, while satisfaction was often higher for PHP participants during follow-up periods lasting 7 to 12 months after discharge. More recent adult studies have also reported significant reductions in depression and anxiety in both in-person and virtual PHP settings. The systematic review indexed by PubMed provides the broader comparison.
| Candidate Profile | Why PHP Fits |
|---|---|
| Severe depression without a need for inpatient containment | Daily monitoring and therapy can address worsening mood, hopelessness, and impaired functioning |
| Generalized anxiety or panic symptoms | Repeated skills practice can support exposure, regulation, and coping between sessions |
| PTSD or trauma-related symptoms | A structured schedule can provide stabilization before deeper trauma work |
| Bipolar disorder with ongoing outpatient safety | Psychiatric oversight and routine can help monitor mood changes and treatment response |
| Veteran returning to civilian routines | Mission-focused structure and accountability can support adjustment while preserving home life |
| Professional or caregiver with a stable home plan | Day treatment offers intensive support without an overnight stay |
| Person stepping down from inpatient care | PHP can create a supported transition before less frequent treatment |
PHP may be a step up when weekly therapy hasn't stopped deterioration, panic is interfering with basic responsibilities, medication changes require close observation, or a person cannot reliably use coping skills alone. It may be a step down after inpatient care when the immediate crisis has improved but the person still needs daily clinical contact.
Active suicidality with an inability to remain safe, severe medical instability, psychosis requiring containment, or an unsafe home environment may indicate that inpatient care is more appropriate. Families shouldn't make that decision by themselves. A confidential assessment, such as the guidance described in Cedar Hill's higher level of care resource, can clarify the safest setting.
Getting Started at Cedar Hill Behavioral Health
For Massachusetts families, access often feels as urgent as the clinical decision. Cedar Hill Behavioral Health is a veteran-owned treatment center in Southborough that offers PHP, IOP, and outpatient services. Its admissions process is designed to begin with a practical conversation rather than asking a distressed family to handle every insurance and scheduling question alone.
What the admission process involves
The first step is a phone call or online inquiry. An admissions specialist gathers basic information about symptoms, current safety, treatment history, scheduling needs, and the level of support available at home. The clinical team then conducts a confidential screening to determine whether PHP appears appropriate or whether another service is safer.
Insurance verification follows. The admissions team reviews benefits, explains expected coverage, and helps address authorization or paperwork requirements. Families can ask about self-pay options and payment arrangements before treatment begins. Availability and authorization can vary, so same-day admission depends on clinical appropriateness, scheduling, and payer requirements.
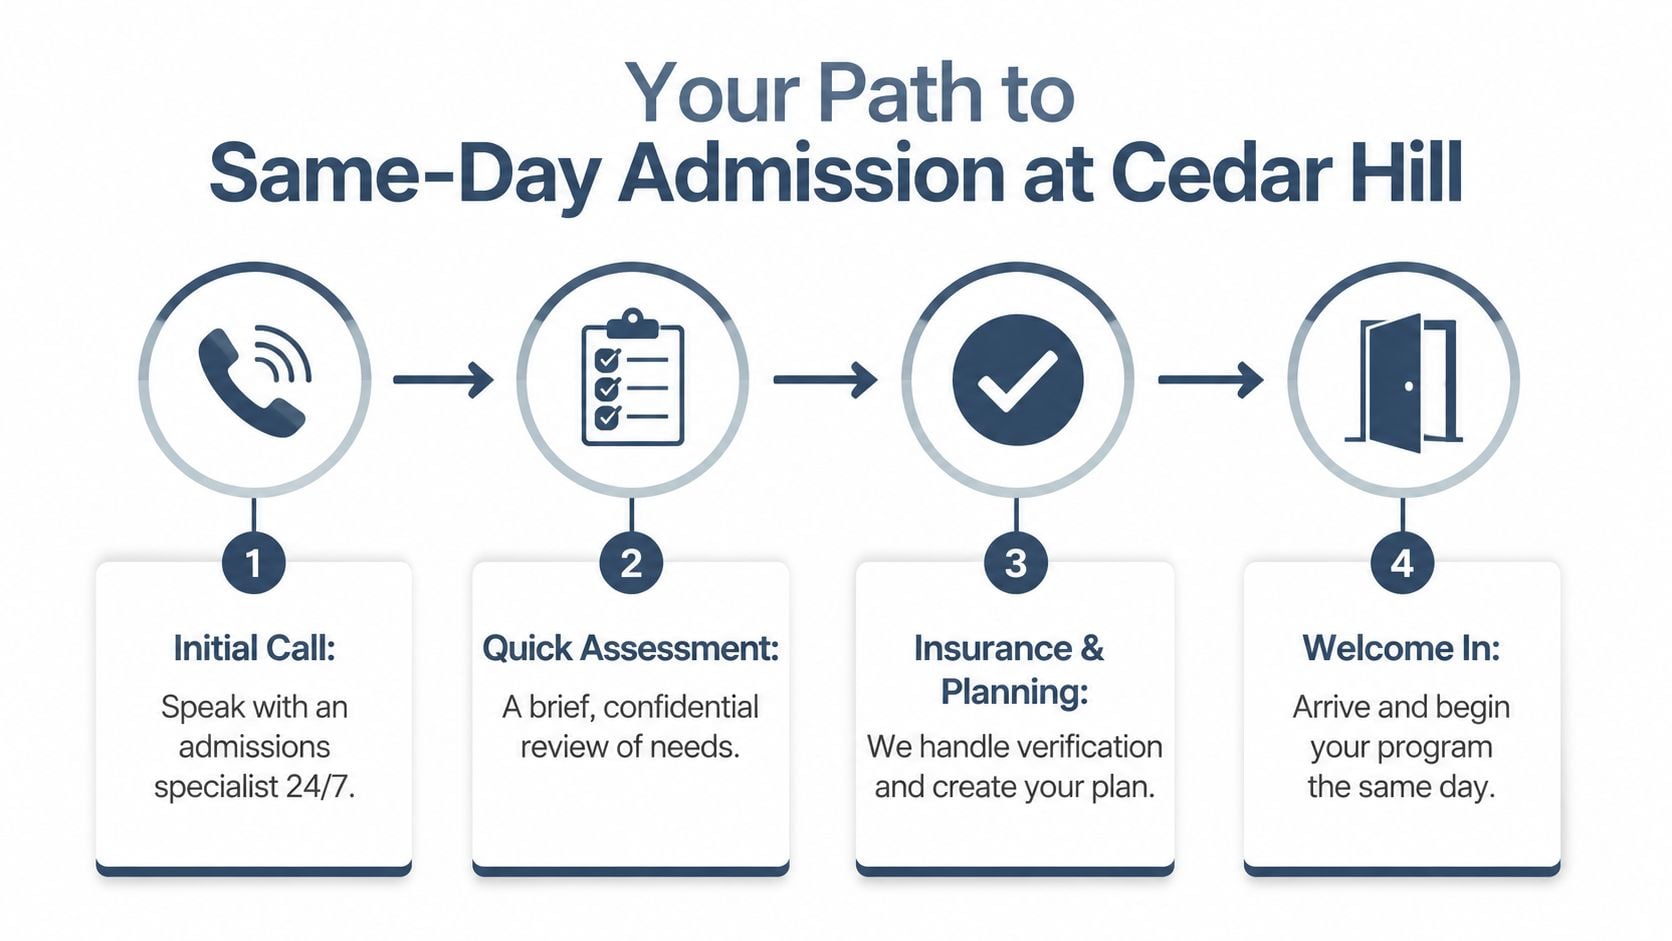
When admission is approved, day one generally includes orientation, intake assessments, introductions to the treatment team, and participation in the therapeutic schedule when clinically appropriate. The patient may meet with a therapist, psychiatric provider, or other licensed professionals to establish immediate goals and safety procedures.
What care may include
Cedar Hill's treatment approach can include:
- Cognitive behavioral therapy: Identifying thought patterns that intensify depression, anxiety, or avoidance.
- Dialectical behavior therapy: Practicing emotional regulation, distress tolerance, mindfulness, and interpersonal effectiveness.
- EMDR: Using a trauma-focused approach when clinically appropriate and when stabilization supports that work.
- Group and individual therapy: Combining shared skills practice with private attention to personal goals.
- Medication management: Reviewing medication effectiveness, side effects, adherence, and possible adjustments.
- Family participation: Helping loved ones understand warning signs, communication strategies, and the home safety plan.
The veteran-owned model informs a culture centered on accountability, service, consistency, and mission-driven care. That doesn't mean every patient shares a military background. It means the treatment environment can emphasize clear expectations while maintaining individualized, respectful support.
Families should ask about the facility location, daily schedule, transportation, meals, medications, clothing, technology requirements for virtual care, and how family meetings are arranged. The same-day mental health admission process in Massachusetts can help prospective patients understand what to expect before making contact.
Common Questions About PHP Treatment
Can PHP happen virtually?
Virtual PHP may be available, depending on the provider, diagnosis, safety plan, state requirements, technology, and home environment. Research involving adolescents found higher attendance in virtual PHP than among in-person peers, along with higher caregiver attendance at family meetings, while satisfaction remained high in both formats. The APA-indexed study on virtual and in-person PHP highlights why access and caregiver participation deserve attention.
Virtual care isn't automatically suitable for everyone. Patients need privacy, reliable connectivity, a safe place to participate, access to emergency support, and a plan for what happens if risk increases. Clinicians must also determine whether the patient can engage consistently outside a clinic.
How long does PHP last?
There isn't one universal duration. CMS states that it doesn't impose specific limits on how long PHP services may be covered, so coverage remains connected to medical necessity and continued clinical need. CMS payment guidance explains this flexibility.
Discharge decisions should reflect symptom measures, safety, participation, functioning, medication response, and the person's ability to use skills outside treatment. The next step may be IOP, standard outpatient therapy, medication management, family support, or another service.
What happens after PHP ends?
PHP shouldn't be treated as an isolated event. A discharge plan may include relapse warning signs, coping tools, crisis contacts, medication follow-up, therapy appointments, and specific instructions for stepping care back up if symptoms return.
The evidence on long-term outcomes remains limited, especially for adolescents. A systematic review found improvement from admission to discharge in all included studies, but only one study used a comparison group and only one included follow-up data, leaving uncertainty about how consistently gains persist after discharge. The adolescent PHP review supports careful aftercare rather than assuming discharge equals recovery completion.
Can patients work or attend school?
Some patients can maintain selected responsibilities, but a full PHP schedule may make ordinary work or school attendance difficult. The treatment team can help document clinical needs and discuss workplace or school accommodations. FMLA or disability paperwork may be relevant, but eligibility and approval depend on the employer, insurer, clinician documentation, and applicable rules.
Does PHP include medication management and insurance support?
Psychiatric evaluation and medication management are commonly integrated when clinically indicated. Insurance coverage varies by plan, diagnosis, authorization rules, and documentation of medical necessity. The admissions team should verify benefits before treatment and explain what happens if authorization changes.
A return to PHP is possible when symptoms rise again and the person remains appropriate for outpatient treatment. Re-entry isn't a failure. It can be a timely response that prevents a more severe crisis.
Take the Next Step Toward Structured Mental Health Support
PHP gives people a structured path between weekly therapy and inpatient hospitalization. It offers daily therapeutic contact, opportunities to practice skills in real time, psychiatric support when needed, and a planned route toward less intensive care. The approach is especially useful when symptoms are serious but the person can remain safe at home with an appropriate plan.
Massachusetts residents can contact Cedar Hill Behavioral Health to ask about same-day admission, confidential insurance verification, PHP availability, virtual or in-person participation, and the practical requirements for starting care. A family member can make the first call on behalf of someone who feels overwhelmed. The admissions team can explain what information is needed, whether the program appears clinically appropriate, and what alternatives exist if PHP isn't the safest fit.
Reaching out doesn't commit a person to treatment. It creates a clear next step when uncertainty has become part of the crisis. PHP is not a last resort. For many people, it's a proactive level of support that helps stabilize symptoms and build a sustainable recovery plan.
Cedar Hill Behavioral Health provides structured PHP care in Massachusetts, with individualized therapy, group treatment, psychiatric support, and help verifying insurance benefits. Visit Cedar Hill Behavioral Health or call (508) 310-4580 to request a confidential assessment and discuss whether same-day admission is appropriate.








