

Someone in Massachusetts finally gets serious about care on a Tuesday night, opens a phone, types therapy options near me, and immediately gets buried in a mess of names, maps, and vague promises. The main question is never just who is closest. It's what level of care fits, how fast admission can happen, and whether insurance will slow the whole thing down.
That's the right way to search. Clinical fit comes first, then access, then cost, then convenience. A family that starts with distance alone usually wastes time on calls that go nowhere, while a family that starts with symptom severity can move much faster toward the right program.
Table of Contents
- Why Searching for Therapy Options Near Me Feels Harder Than It Should
- Understanding the Levels of Care Available Locally
- Comparing PHP IOP and Outpatient Side by Side
- How to Search and Filter Local Providers Effectively
- Insurance Verification and Same-Day Admission Logistics
- Real-World Scenarios for Choosing a Local Program
- Common Misconceptions About Local Therapy Access
- Your Next Step Toward Starting Care This Week
Why Searching for Therapy Options Near Me Feels Harder Than It Should
A Massachusetts adult can do everything right, decide to get help, make the search, and still feel stuck in the first five minutes. The screen fills with provider profiles, but the profiles rarely answer the question that matters most: does this person need PHP, IOP, or standard outpatient therapy? That missing answer is why so many searches feel frustrating instead of reassuring.
The deeper problem is access. In the U.S., 23.4% of adults experienced mental illness in 2024, equal to 61.5 million people, and 5.6% experienced serious mental illness, or 14.6 million people. Yet only 52.1% of adults with any mental illness received treatment, and only 70.8% of those with serious mental illness received treatment, while more than 120 million people live in a designated Mental Health Professional Shortage Area, which helps explain why local access, wait times, and same-day availability matter so much (NAMI).
Why a provider list isn't enough
A directory can tell someone who practices nearby. It usually can't tell them whether the clinician can absorb the current level of symptoms, what the wait is, or whether the program accepts the plan the family has. That's why a useful search starts with fit, not just proximity.
Therapy use has risen, but access is still uneven. A national analysis reported that outpatient talk therapy participation among U.S. adults increased from about 16.5 million people in 2018 to nearly 22 million in 2021, and CDC data show that in 2019, only 19.2% of adults received any mental health treatment in the prior 12 months, including 9.5% who received counseling or therapy from a mental health professional (NPR). That demand explains the bottleneck.
Practical rule: if the person is struggling to work, parent, sleep, or stay safe, the search should move beyond “near me” and into level-of-care triage immediately.
The most honest search question is this. What can start this week, and what intensity is clinically appropriate today?
Understanding the Levels of Care Available Locally
Mental health care works best when it's treated like a ladder, not a menu. PHP, IOP, and outpatient are different rungs, and the right rung depends on how much structure the person needs to stay stable. If that match is wrong, the family either overpays for intensity they don't need or under-treats symptoms that clearly need more support.
PHP is the highest rung short of inpatient care
Partial Hospitalization Program, or PHP, is the most structured outpatient level. It usually means several clinical hours across most weekdays, with group therapy, individual therapy, family involvement when appropriate, and medication support if it's part of the plan. PHP fits people whose symptoms are too disruptive for weekly therapy, but who don't need overnight containment.
IOP gives serious support with more flexibility
Intensive Outpatient Program, or IOP, sits in the middle. It's still structured, but it leaves more of the day open for work, school, or caregiving. For many adults, that difference is the whole decision. IOP is often the right call when symptoms are escalating, but the person can still stay in the community and use daily routines as part of recovery.
Outpatient is the lighter step
Outpatient therapy usually means weekly individual sessions, sometimes with medication management, and in some programs optional group or family sessions when clinically appropriate. Cedar Hill Behavioral Health describes outpatient care that includes weekly individual therapy, optional group therapy, and family therapy when appropriate and with the patient's consent, which is exactly the kind of structure a lower-acuity client may need after a more intensive stepdown or during steadier periods (Cedar Hill outpatient care).
Step down when the person can keep appointments, use coping skills between sessions, and stay safe without daily clinical contact. Step up when those things stop being true.
For families comparing levels, a good outside reference on how intensity differs across settings is the Children Psych treatment guide, which helps clarify why “outpatient” is not one single category. The important point is simple. Match the setting to symptom severity, not to convenience alone.
Comparing PHP IOP and Outpatient Side by Side
A clean comparison saves families from making five calls just to learn the basics. The table below uses the same criteria across the three levels so the difference is obvious at a glance. For a Massachusetts family trying to decide what kind of help belongs on the calendar this week, that clarity matters more than marketing language.
| Criteria | PHP | IOP | Outpatient |
|---|---|---|---|
| Hours per week | Highest outpatient intensity, usually weekday-based and close to a full clinical day | Moderate intensity, several hours on selected days | Lowest intensity, typically weekly sessions |
| Structure | Highly structured, with frequent clinical contact | Structured, but leaves more of the day open | Flexible and lighter touch |
| Who it fits best | People who need close support to stabilize symptoms | People who need real support while still handling parts of daily life | People who are stable enough for weekly care or stepdown support |
| Cost position | Usually the most resource-intensive outpatient option | Middle ground between PHP and standard therapy | Usually the least intensive option |
| Typical use | Stabilization, symptom containment, and stepdown from a higher level if needed | Ongoing stabilization while preserving work or family routines | Maintenance, follow-up, or lower-acuity treatment |
For readers comparing program details more closely, the Cedar Hill IOP overview helps explain why IOP is often the practical middle ground. It's not a lighter version of real treatment. It's a different clinical tool.
How to choose without second-guessing
If symptoms are affecting safety, work attendance, or parenting, PHP deserves serious consideration. If the person can function but needs a strong clinical container, IOP usually makes more sense. If the person is stable, motivated, and mainly needs continuity, outpatient is the cleaner fit.
The wrong level of care can waste a week. The right one can change the shape of the month.
That's why the comparison matters. Families shouldn't ask only, “Who has an opening?” They should ask, “Which level can support this level of distress?”
How to Search and Filter Local Providers Effectively
Distance alone is a weak filter. A provider can be close and still be wrong for the diagnosis, wrong for the insurance, wrong for the schedule, or wrong for the needed level of care. The smarter approach is to search with clinical and access filters at the same time.
Set the filters before reading profiles
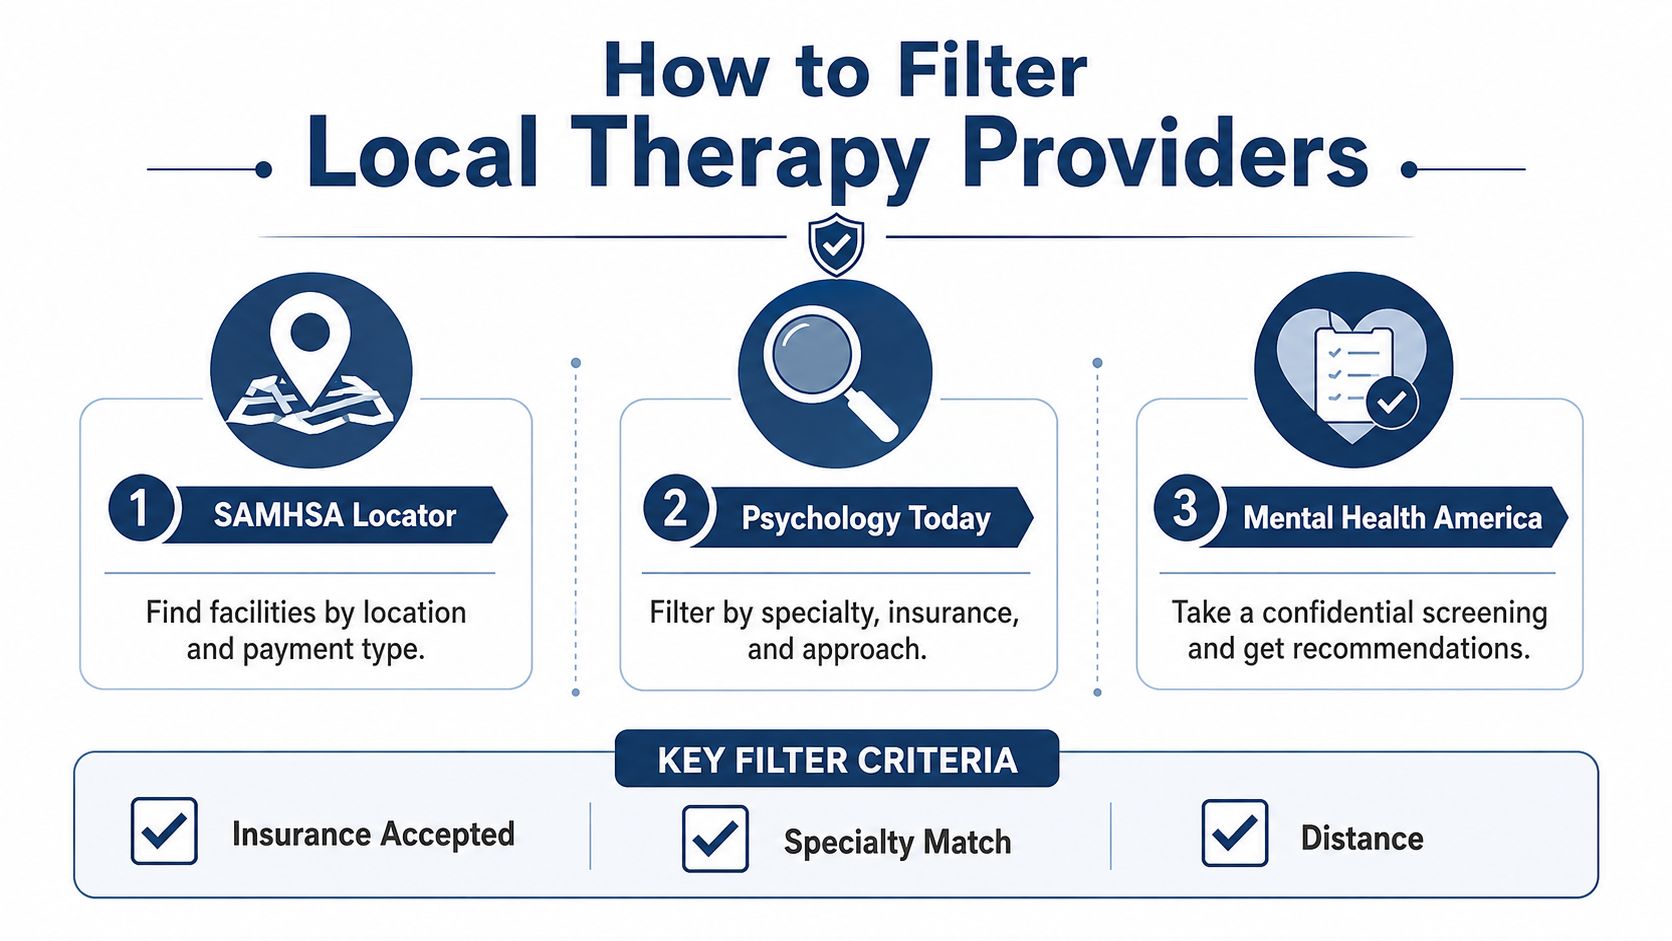
Mental Health America points people toward SAMHSA's treatment locators and therapy directories that allow searches by zip code or city, specialty area, fees, insurance acceptance, sliding-scale availability, credentials, and contact information (MHA finding therapy). That matters because the odds of finding a useful match go up when the search narrows both access variables and treatment variables.
Use this order:
- Insurance first. If the plan matters, check whether the provider accepts it before spending time on bios.
- Specialty second. Anxiety, OCD, PTSD, mood disorders, and family needs are not interchangeable.
- Modality third. Some people need group-based structure; others need individual-only care.
- Distance last. A slightly farther provider who can treat the condition is better than a nearby mismatch.
What to look for inside a profile
In-person therapy directories can be filtered by location, insurance accepted, specialty areas, therapeutic approaches, and whether a provider offers in-person sessions. Profiles may also include credentials and areas of expertise, and users can contact therapists directly to schedule an initial consultation. That combination is what turns a directory from a list into a decision tool.
The search should be ruthless about fit. If the person needs a structured level of care, don't waste time on a long list of low-intensity outpatient names. If insurance is a make-or-break issue, don't keep reading profiles that never answer the question.
Insurance Verification and Same-Day Admission Logistics
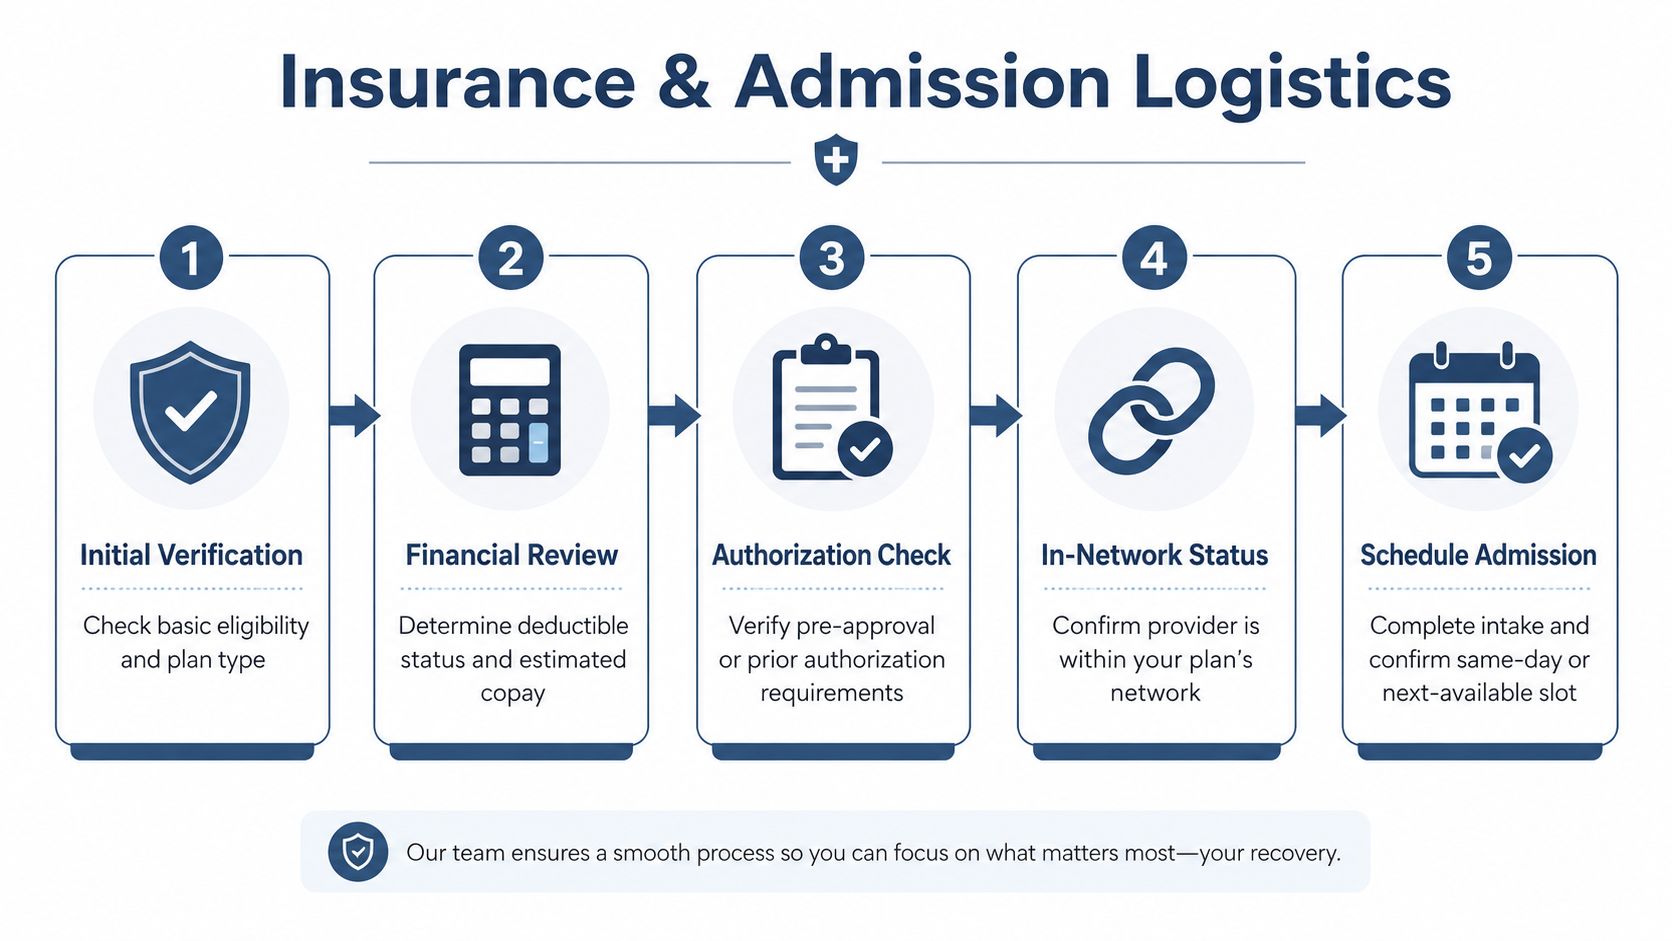
Families lose time here because they start with the wrong question. They find a program they like, then spend days trying to figure out whether the plan is active, whether prior authorization is required, and whether the provider is in network. A good admissions team takes that work off the family's plate and handles the coverage check before anyone wastes time on a dead end.
What benefits verification actually checks
Benefits verification should confirm eligibility, deductible status, authorization requirements, and in-network status. Those four items determine whether care can start quickly and what the family should expect financially. If a center offers instant verification, that is not a perk. It is usually the fastest way to find out whether care can begin this week or whether the plan will slow everything down.
Have these ready before the call:
- Insurance card with the current plan information.
- Photo ID for identity matching.
- Current prescribing or referral notes, if they exist and are relevant.
- A clear description of symptoms, especially if the person needs PHP or IOP rather than routine therapy.
Admissions coordinators move faster when the call is specific. Saying, “The person needs help with escalating anxiety and can't wait weeks,” is much more useful than just asking for availability.
Benefits questions also go more smoothly when the family knows exactly what to ask. The Reflections insurance guide for executives is a useful reference point for how coverage conversations are usually handled. Ask whether the plan is active, whether a deductible still applies, whether prior authorization is needed, and whether the requested level of care is in network. Those are the questions that decide whether the process moves today or stalls.
How same-day admission can happen
Same-day admission happens only when the center can complete its own clinical intake, verify benefits quickly, and place the person in an opening that matches the right level of care. The person usually completes screening, reviews the plan, and then moves to the first visit or start date based on clinical fit and authorization. That process is practical, not mysterious.
A center can only offer same-day start if the intake team gets enough information up front. If the person needs PHP, the team has to confirm that the symptoms really call for a higher level of structure. If the person fits IOP or outpatient therapy, the team should say that plainly instead of forcing a higher-intensity start that does not match need. Same-day admission is about matching severity to the right slot, then clearing the insurance pieces without delay.
Cedar Hill Behavioral Health also offers a free insurance verification for therapy, which is exactly the kind of first step that cuts down delay. If self-pay is the only option, ask about payment plans instead of assuming care is out of reach. That question belongs on the first call, not the fifth.
Real-World Scenarios for Choosing a Local Program
Three Massachusetts adults can look at the same directory and need completely different care. That's why the strongest search strategy starts with the person's actual functioning, not the most attractive website. Severity, schedule, and safety drive the decision.
A veteran with PTSD and a need for trust
A veteran dealing with PTSD may need more than weekly talk therapy if nightmares, hypervigilance, and avoidance are interfering with daily life. A veteran-owned center can matter because the tone of care feels more direct and respectful, and trauma-focused services such as EMDR become part of the conversation early instead of later. PHP fits if symptoms are overwhelming; IOP fits if the person can stay grounded at home but needs frequent contact.
A working parent whose anxiety is spreading
A parent who's still working but missing sleep, losing concentration, and falling behind on basic responsibilities usually doesn't need the lightest level of care. That person often needs IOP, because it gives enough structure to interrupt the spiral without forcing a full stop to work or caregiving. Weekly outpatient therapy may be too thin if the anxiety is escalating quickly.
A college-aged adult with OCD
A student with OCD who can still attend classes but is spending hours on rituals and reassurance-seeking may stabilize in outpatient care if the symptoms are still contained. If the compulsions are getting harder to interrupt, though, the family should look one rung higher. The right choice is the one that keeps the student enrolled while reducing the behaviors that are hijacking the day.
The program should match the problem, not the idealized schedule.
Cedar Hill Behavioral Health in Southborough, Massachusetts offers PHP, IOP, and outpatient care in one setting, which makes step-up and step-down decisions simpler when symptoms change. That continuity matters when families don't want to restart the search every time the clinical picture shifts.
Common Misconceptions About Local Therapy Access
A lot of people stay stuck because they believe the wrong thing about access. Those beliefs sound reasonable, but they don't hold up in real admissions work.
“Every center has a long waitlist”
Not true. Some programs do run long waits, but some centers can move quickly when the level of care, insurance, and schedule line up. Same-day admission exists because some teams handle screening and intake internally rather than outsourcing the process.
“Real therapy means one session a week”
That's too narrow. For many diagnoses, especially when symptoms are escalating, structured group treatment and higher-touch programs are clinically important. Weekly therapy is useful, but it isn't always enough to stabilize someone who's sliding.
“Insurance is the patient's job alone”
That's backwards. Admissions teams should help with benefits verification, explain whether authorization is needed, and translate the plan into plain language. The family should provide the card and the basic information, then let the center do the verification work.
The operational truth is simple. Access is a process, not a guess. Families move faster when they stop assuming they have to solve everything before making the first call.
Your Next Step Toward Starting Care This Week
A Massachusetts family that has already identified the likely level of care, filtered for insurance and specialty, and learned how admission works is ready for the final step. That step is a direct admissions call, not more scrolling. The goal is to confirm fit, verify benefits, and get a real start date on the calendar.
Cedar Hill Behavioral Health is located at 120 Turnpike Rd., Suite 120, Southborough, MA. Their team can help with PHP, IOP, and outpatient care, plus confidential benefits verification and same-day admission conversations when clinically appropriate. Call (508) 310-4580 and ask for prompt guidance on starting care this week.
If the person is still unsure, use the free online depression test or the adult ADHD self-screen as a first step. If the symptoms are already interfering with work, sleep, school, or family life, don't wait for a perfect moment. That moment usually doesn't come.
Cedar Hill Behavioral Health helps Massachusetts adults move from searching to starting care with PHP, IOP, and outpatient options in one place. If the next step is a real conversation about fit, benefits, and admission timing, visit Cedar Hill Behavioral Health and ask for a confidential call today.








