

A family usually starts searching for a personality disorder treatment center after the same painful pattern repeats. There's a blowup at home, a frantic late-night call, a promise to start over, and then another crisis before anyone has time to think clearly. The right center doesn't just offer a place to talk, it gives the family a fast, structured path into care that matches how severe the symptoms are right now.
That distinction matters because personality disorders aren't rare, and they're not always being treated. The National Institute of Mental Health estimates that 9.1% of U.S. adults had any personality disorder in the past year, and 1.4% had borderline personality disorder. Yet only 39.0% of adults with any personality disorder and 42.4% of adults with borderline personality disorder reported receiving any mental health treatment in the past 12 months, which means a significant majority of those affected were not in care during that period, according to NIMH personality disorder statistics.
Table of Contents
- Understanding What a Personality Disorder Treatment Center Does
- Evidence-Based Treatments That Actually Work
- Choosing the Right Level of Care for Your Situation
- How to Evaluate and Choose a Treatment Center
- What to Expect During Intake and Your First Weeks
- Navigating Insurance Coverage and Payment Options
- Veteran-Focused Care and Taking Your Next Steps
Understanding What a Personality Disorder Treatment Center Does
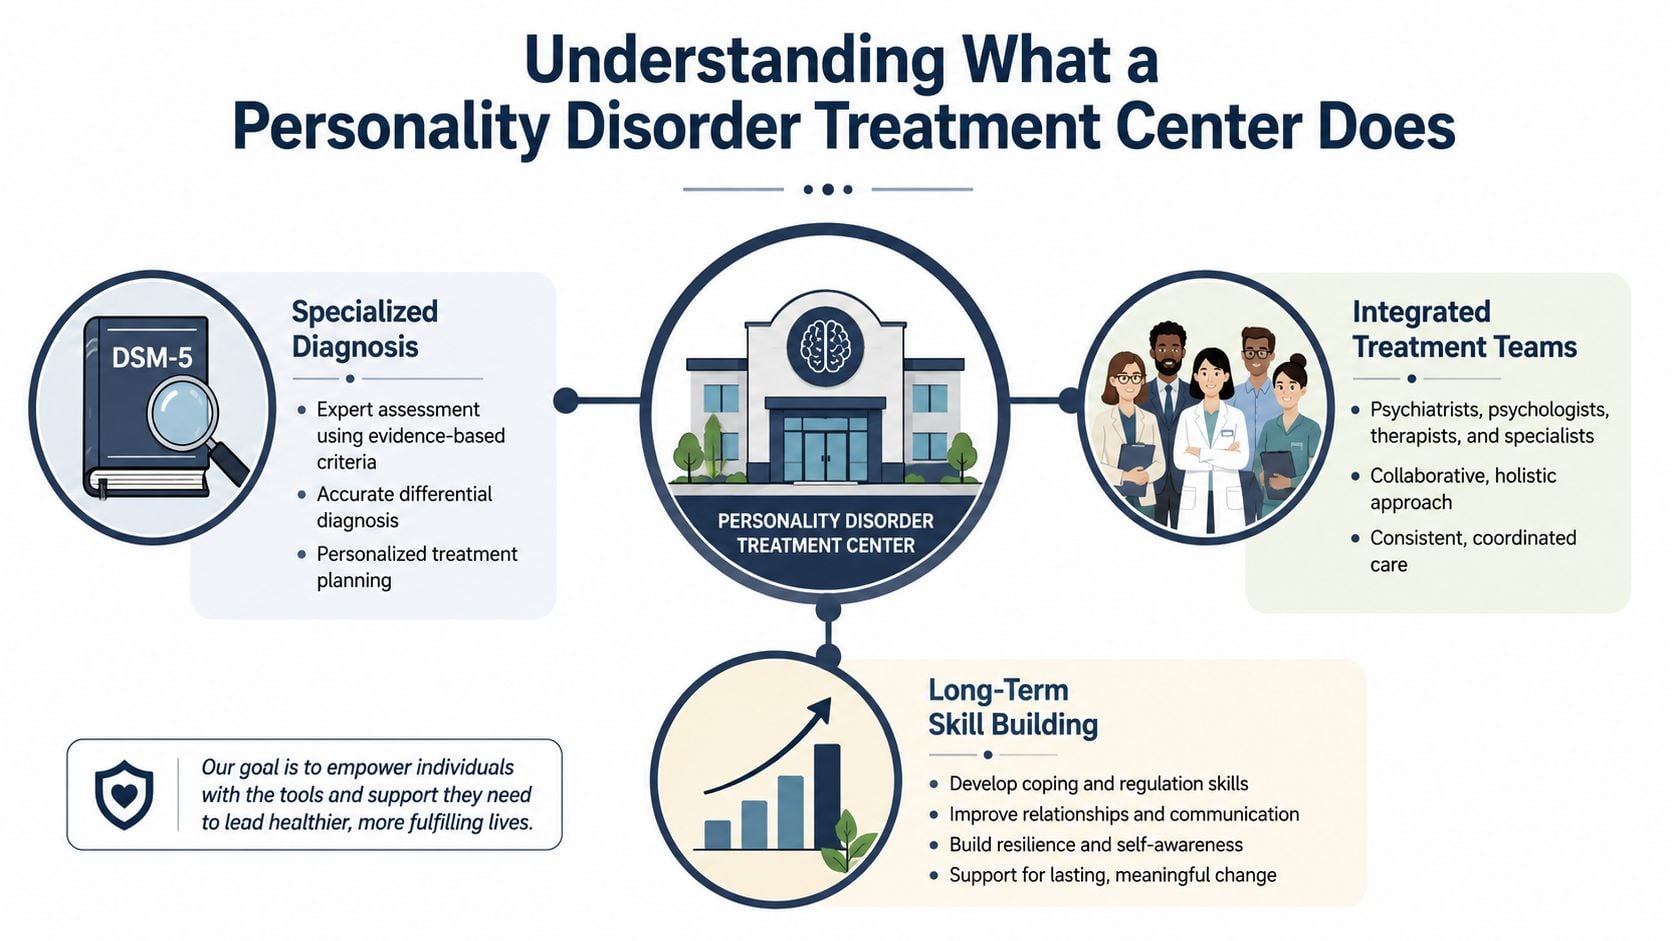
A specialized center handles a very different problem than a general counseling office. Families usually call after they've already tried reassurance, one-off therapy appointments, or a short hospital stay, and those steps haven't held the line. What they need next is not more vague advice, it's a setting that can organize diagnosis, safety planning, and skill-building around a long-term pattern of emotional and relational instability.
What changes in a specialty setting
A personality disorder treatment center usually starts with a more careful assessment than a standard intake. That matters because symptoms often overlap with depression, trauma, substance use, and other psychiatric concerns, and treatment only works when the team sees the full picture. A center's job is to coordinate that picture across psychiatry, therapy, group work, and family involvement instead of isolating each issue.
A common misconception is that personality disorders are somehow untreatable. That isn't supported by the evidence. A major review found large pre-post improvements across studies, with mean effect sizes of 1.11 on self-report and 1.29 on observational measures, and in four studies about 52% of patients who stayed in therapy no longer met full personality-disorder criteria after an average of 1.3 years, which points to the need for structured, long-horizon care rather than brief symptom-only management, as reported in the review on psychotherapy for personality disorders.
Practical rule: if a program talks only about “coping better” but can't explain how it handles self-harm risk, family strain, and step-down care, it's probably too thin for this diagnosis.
Families in Massachusetts often ask whether a center can help without turning care into a maze. An integrated option such as Cedar Hill Behavioral Health's complete guide to behavioral health care can be useful when the problem isn't just one symptom, but a whole pattern that needs coordinated treatment. A good center creates consistency, clear expectations, and enough structure for the person to practice new behavior in real life instead of only discussing it.
Evidence-Based Treatments That Actually Work
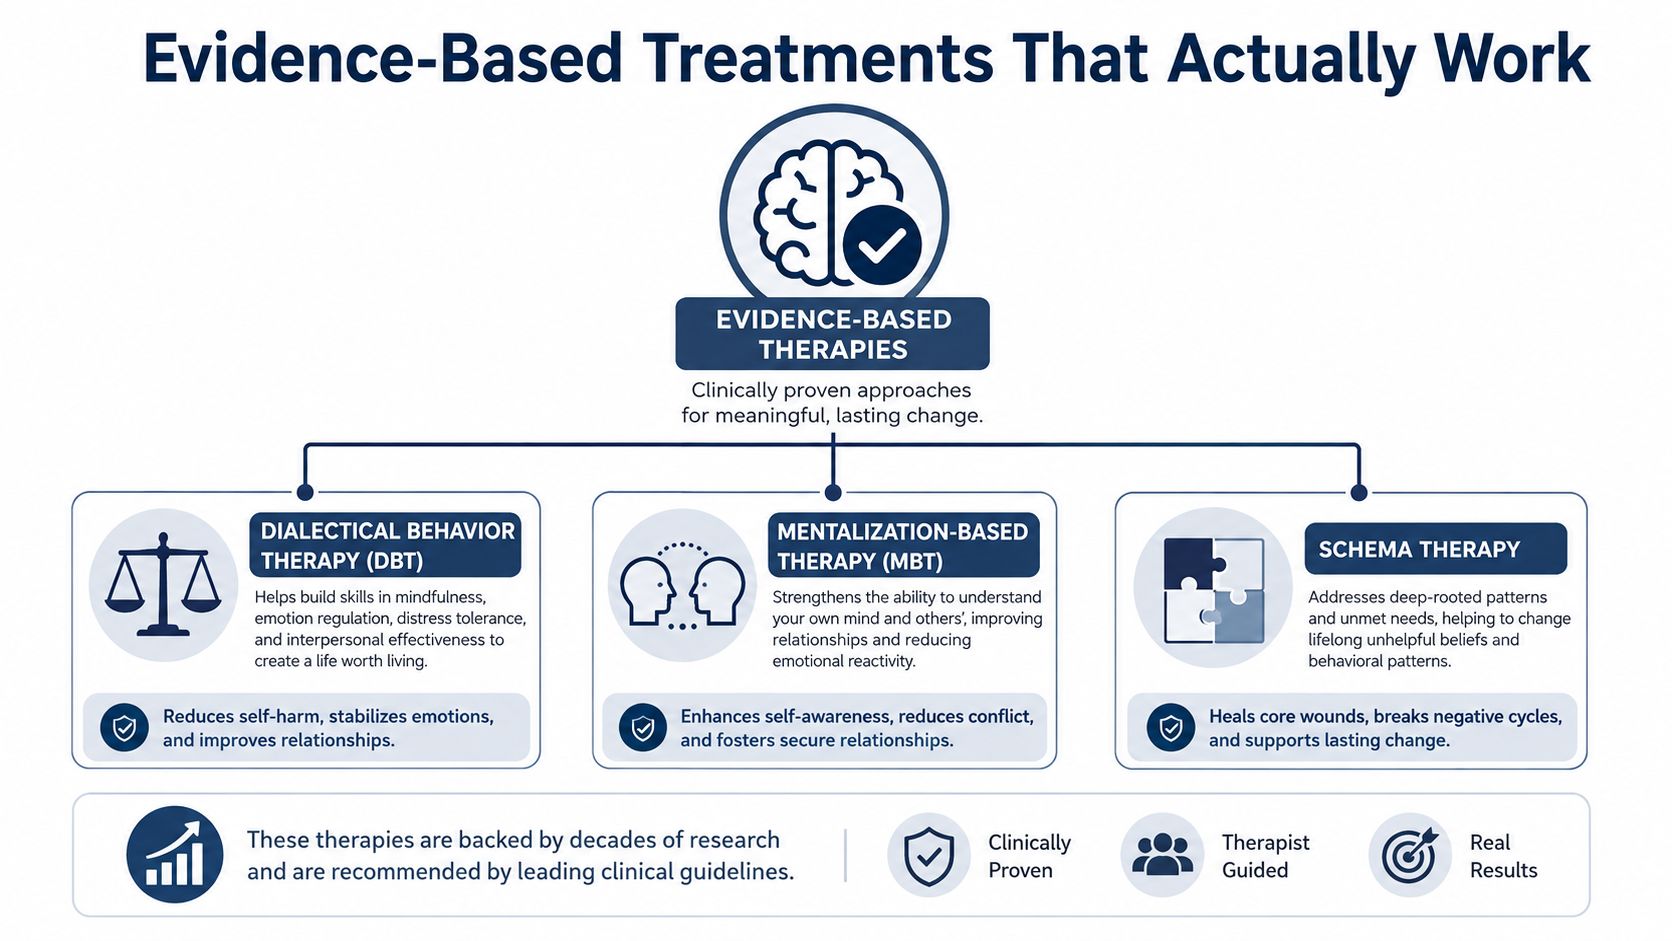
The best centers don't rely on a single therapy label. They build a plan around the person's actual symptoms, and they use psychotherapy as the core intervention. That matters because treatment evidence supports structured psychological care, not medication alone, and it also supports community-based settings when the person doesn't need 24-hour supervision.
What the treatment mix should actually include
Dialectical Behavior Therapy, or DBT, is often the anchor for borderline personality disorder care because it gives patients skills, not just insight. The practical value is in the structure. Skills training, individual sessions, and between-session coaching help patients notice triggers earlier and respond differently when emotions spike. A center that understands DBT as a system, not a slogan, is much more likely to help than one that only advertises the name.
Cognitive Behavioral Therapy can still play a major role, especially when distorted thinking patterns feed shame, fear, or impulsive behavior. Trauma-focused work can matter too when the history includes abuse, neglect, or other overwhelming experiences, because untreated trauma often keeps symptoms active. The key is coordination. Therapies should fit together instead of competing with each other.
For a more practical look at how clinicians organize evidence-based care, it can help to browse the EBP nursing guide. The point isn't to become a clinician, it's to see what a real evidence-based framework looks like when people are making decisions under stress.
Medication and therapy should serve different jobs
Medication management can support treatment, but it shouldn't be sold as the solution to the personality disorder itself. The literature on service organization emphasizes benefit from psychological and psychosocial intervention in community-delivered care, and outpatient or community-based programs can reduce borderline-personality symptoms, anxiety, depressive symptoms, and global psychiatric symptoms compared with non-active controls at end of treatment, according to the systematic review and meta-analysis on community-based treatment. That's why thoughtful medication review is best used to stabilize sleep, mood, or anxiety enough for therapy to work.
CEDAR HILL DBT therapy interventions can be one example of how a center may organize that support around skill practice, though the central question is always whether the plan stays coordinated across the whole team.
Treatment works best when the center treats symptoms, relationships, and daily functioning as one connected problem.
Choosing the Right Level of Care for Your Situation
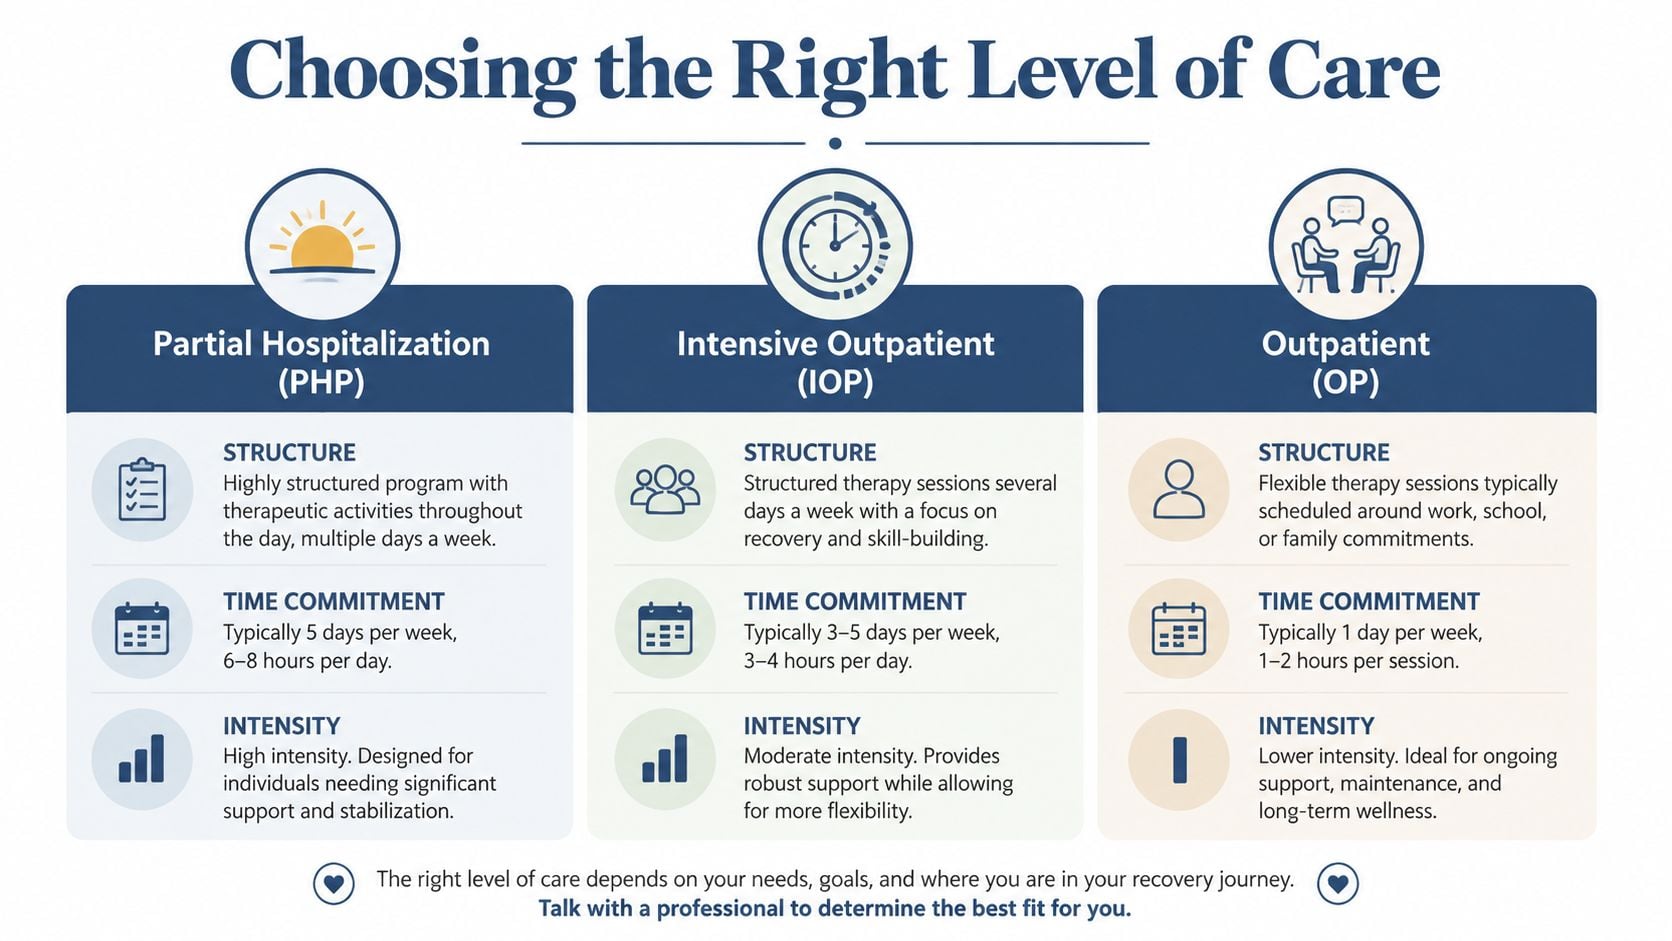
A family can do everything right and still end up stalled at the wrong level of care. A person is getting more reactive, sleep is falling apart, or self-harm urges are becoming harder to contain, and the question becomes simple: what setting can hold the situation safely right now? PHP, IOP, and OP serve different stages of symptom escalation, and the right choice is usually the one that matches current risk, daily functioning, and how quickly the team can adjust if things worsen.
Why PHP, IOP, and OP fit different stages of symptom escalation
PHP fits when the person needs a full daytime structure but does not need 24-hour inpatient supervision. It gives the treatment team enough contact to respond when symptoms are intensifying, while still letting the person go home at night, which can help preserve family involvement and daily routine. That combination matters when the goal is stabilization without pulling someone into a hospital stay that may be more restrictive than necessary.
IOP is the next step when symptoms are still interfering with life, but they are somewhat more contained. A person may need more than weekly therapy, yet may still be able to manage home, work, or school with a focused treatment schedule. OP is the lighter layer, usually appropriate when safety is steadier and the person needs ongoing therapy and medication follow-up without a heavy weekly commitment.
A practical way to sort these levels is to use a clear step-down or step-up pathway. This overview of mental health program levels of care at Cedar Hill Behavioral Health shows how programs can shift care as symptoms change, which is often what families need when they are trying to get help quickly and avoid losing momentum. The strongest programs do not trap a person in one track. They move between levels as needed, because symptoms can flare fast under stress.
Capacity is part of the reality, too. A German survey of DBT inpatient and day-clinic facilities found 527 treatment places serving about 2,310 patients per year, with a mean pre-treatment wait of 14.3 weeks, and it estimated about 820 borderline patients for each existing inpatient/day-clinic DBT place in Germany in 2011, showing how tight access can be, according to the survey in PubMed.
What usually pushes the decision upward
- Escalating self-harm or crisis behavior: When urges are rising and the home setting cannot reliably contain them, a higher level of care is usually the safer move.
- Poor daily functioning: If work, sleep, family roles, or basic routines are falling apart, weekly therapy may be too light.
- Weak support at home: The less stable the home setting, the more structure the person is likely to need.
A selective stepped model usually makes more sense than starting with hospitalization every time someone needs fast help but not an inpatient unit.
The service gap is real. Care-seekers repeatedly ask for outpatient or intensive outpatient care more than any other service, along with family services and crisis intervention that many systems still do not provide well, according to the service-organization review. A center that offers a full continuum is easier to use than one that forces a hard reset each time symptoms change.
How to Evaluate and Choose a Treatment Center

A parent may hear that a loved one needs a personality disorder treatment center and still have no clear sense of what to ask first. The practical question is simple: can this program get the person into the right level of care quickly, and can it handle the complications that usually come with personality disorders, such as self-harm risk, family conflict, substance use, or a mood disorder that is making symptoms harder to control?
What strong programs usually have
A strong program can describe the therapies it uses and how those therapies are delivered in real life. It should also explain how staff respond to emotional dysregulation, relational conflict, and self-harm risk without making the setting feel punitive or chaotic. Family involvement should be part of the treatment plan, because the home environment often shapes whether care holds after discharge.
The other marker is continuity. A center should be able to explain what happens after the first admission decision, how PHP, IOP, and OP fit together, and what the step-down path looks like if symptoms improve or flare again. The psychotherapy literature points to meaningful change happening over time, so a program that only talks about intake and discharge may be missing the realities of treatment. When a team cannot explain follow-up planning, it often does not have a workable model for the pace this diagnosis usually requires.
What to ask about when evaluating a personality disorder program
- How do you assess risk and decide between PHP, IOP, and OP? The answer should sound clinical and specific, not promotional.
- What happens if symptoms worsen after admission? A good center should be able to describe its escalation pathway.
- How do you involve family members? Families need practical guidance, not just reassurance.
- How is medication managed alongside therapy? The team should explain how it supports, not replaces, psychotherapy.
Cedar Hill Behavioral Health is one Massachusetts option that offers same-day admissions, instant benefits verification, and a full continuum of care including PHP, IOP, and OP. That matters when a family cannot afford to wait while symptoms keep escalating.
Bad fits usually reveal themselves quickly. Programs that promise a quick fix, avoid clear treatment protocols, or cannot explain staff training are worth passing over. The goal is to find a place that can keep a person safe, keep them engaged, and support the next step in care without forcing a reset every time symptoms change.
What to Expect During Intake and Your First Weeks
The first call often feels harder than the first session. Families are usually tired, worried, and unsure whether the person they love will even agree to come in. Once admission starts, a quality center tries to reduce confusion by making the next steps concrete, predictable, and collaborative.

Intake should feel thorough, not rushed
A solid intake usually includes psychiatric evaluation, a look at current symptoms, and a treatment plan built around the person's risk level and daily needs. Families should expect questions about relationships, work, sleep, self-harm history, substance use, and any trauma or mood symptoms that may be driving instability. The point is to understand patterns, not just lists of diagnoses.
Early weeks can feel emotionally intense because structure is new. Group therapy, individual work, skills practice, and medication visits can all happen in close succession, and that pace is intentional. People often feel exposed before they feel better, which is normal when the treatment starts getting under the surface.
What the first phase often looks like
A typical day in PHP is usually more structured than IOP, with more hours and more contact. IOP has a lighter schedule but still keeps treatment active across several days. OP is usually the smallest dose of care, often used once symptoms have steadied enough for maintenance work.
For families who want to understand the testing side of intake, the Orange Neurosciences inventory guide can be a useful reference point for how personality assessment tools help organize information. The exact tools vary by center, but the purpose stays the same, which is to give the team enough detail to make a safer plan.
Progress usually shows up in small, practical changes first, fewer blowups, better follow-through, and more time between crises.
The first weeks are not about “fixing” everything. They're about establishing trust, teaching skills, and making sure the person can stay engaged long enough for those skills to start sticking. When a center does that well, the atmosphere feels firm without being punitive, and the patient begins to experience treatment as support rather than another argument.
Navigating Insurance Coverage and Payment Options
Insurance is one of the biggest reasons people delay care, especially when symptoms are already unstable. Families usually need answers quickly, and they need them before the moment passes and the person decides not to go. The smartest move is to verify coverage before admission, then get clear on what each level of care is likely to require.
What to confirm before the first day
The first question is whether the plan covers PHP, IOP, and OP separately. Those services can differ in authorization requirements, and a family that assumes one approval covers all three can get blindsided later. It also helps to ask about deductibles, copays, and whether the center is in-network or out-of-network.
A good admissions team should explain benefits in plain language and tell the family what documentation may be needed for continued authorization. If the insurer pushes back, the center should have a process for appeals or for helping the family understand the next administrative step. That kind of clarity matters when decisions have to happen fast.
When payment gets complicated
Some families need a bridge while coverage is being sorted out, and others need a different financial path entirely. That's where payment plans or self-pay options can keep treatment moving instead of stopping it at the insurance desk. If the center can't explain these options clearly, the family may spend more time on admin than on care.
For readers who need a broader legal and financial context, Melanson Law Group's mental illness SSDI guide can help frame how disability-related documentation sometimes fits into the larger picture. It's not a substitute for clinical guidance, but it can be useful when family members are trying to stabilize both care and finances at the same time.
Cedar Hill Behavioral Health accepts most major insurance plans, provides instant benefits verification, and offers payment plans for self-pay clients. That combination removes a lot of the uncertainty that keeps people from starting treatment when they need it most.
Veteran-Focused Care and Taking Your Next Steps
Veterans often come into care carrying more than one problem at once. Personality disorder symptoms can sit alongside PTSD, depression, or substance use, and military culture can make it harder to ask for help early. A veteran-owned center can reduce some of that friction by creating an environment that understands service history without turning it into a lecture.
Why the fit matters for veterans
The wrong setting can make veterans feel misunderstood or judged. The right one treats military experience as clinically relevant context, especially when combat stress, moral injury, or long-standing emotional suppression are part of the story. That matters because treatment only works when the person can stay in the room and engage.
A center with same-day access has an advantage when symptoms are escalating. Delays give crises more room to grow, and personality disorder patterns often intensify under stress rather than settling on their own. Fast admission, clear screening, and coordinated care are not convenience features, they're risk-management tools.
What to do next
The most direct next step is to call (508) 310-4580 and speak with admissions staff about current symptoms, level of care, and timing. A confidential online screening can also help organize the conversation before the first call, especially when family members are trying to decide whether PHP, IOP, or OP makes sense. A callback request is useful when the person isn't ready to talk for long but still needs help moving.
Cedar Hill Behavioral Health in Southborough, Massachusetts, offers a veteran-owned setting, same-day admissions, and a full continuum of PHP, IOP, and OP for adults who need structured support without losing all independence. For veterans and families trying to act before the next crisis, that combination can make the difference between waiting and starting.
Cedar Hill Behavioral Health provides structured, evidence-based care for adults who need help choosing the right level of treatment, from PHP to IOP to OP, with fast admissions and insurance support. If the symptoms around personality disorder care are escalating, visit Cedar Hill Behavioral Health or call (508) 310-4580 to speak with admissions about the next step today.








