

OxyContin withdrawal symptoms typically begin 12 to 48 hours after the last dose, peak around days 2 to 3, and the acute phase commonly lasts about 10 to 20 days, while psychological symptoms such as insomnia and cravings can persist for weeks to months. The exact experience varies, so someone counting the hours after a final dose may feel uncertain when symptoms will arrive, how intense they'll become, and whether lingering anxiety or poor sleep means withdrawal is still continuing.
That uncertainty can make stopping feel frightening. A clear timeline helps separate the expected physical process from symptoms that require medical attention, while also showing why support remains important after the worst aches and stomach symptoms ease.
Table of Contents
- What to Expect From OxyContin Withdrawal
- The OxyContin Withdrawal Timeline Phase by Phase
- Why OxyContin Withdrawal Differs From Other Oxycodone
- Factors That Change How Long Withdrawal Lasts
- Acute Withdrawal Versus Post-Acute Withdrawal
- Safe Ways to Manage Withdrawal and Find Treatment
- Warning Signs That Need Immediate Medical Care
What to Expect From OxyContin Withdrawal
A person may spend the first day checking the clock, wondering whether feeling normal means withdrawal has been avoided. With extended-release OxyContin, symptoms often don't start immediately. Withdrawal commonly begins 12 to 48 hours after the last dose, reaches its strongest point around two to three days, and the acute phase often continues for 10 to 20 days, according to the healthdirect overview of opioid withdrawal symptoms.
The first signs can be easy to dismiss. Yawning, sweating, a runny nose, anxiety, chills, and an uncomfortable need to move may appear before the more recognizable flu-like symptoms. As the medication's effect fades, muscle aches, nausea, diarrhea, abdominal discomfort, insomnia, and stronger cravings may follow.
A realistic calendar
The most intense physical discomfort is usually concentrated in the first week, but that doesn't mean every symptom disappears at the same time. Some people continue to experience physical symptoms into the second or third week, particularly after higher doses, long-term use, or exposure to more than one substance.
Practical rule: The end of vomiting, sweating, or muscle aches doesn't automatically mean the recovery process is finished.
The timeline is best understood in two parts. Acute withdrawal is the physical syndrome, including restlessness, aches, gastrointestinal symptoms, and sleep disruption. Post-acute withdrawal involves symptoms such as low mood, irritability, insomnia, anxiety, and cravings that may continue after the body feels physically steadier. The clinical summary of oxycodone detox and withdrawal describes acute withdrawal as generally following a predictable one-to-two-week course, while psychological symptoms may last considerably longer.
Fear often grows when someone expects a short, single event and instead experiences symptoms in waves. Knowing that the process can stretch beyond the first week makes it easier to arrange medical support, protect sleep and hydration, and avoid interpreting lingering cravings as personal failure.
The OxyContin Withdrawal Timeline Phase by Phase
OxyContin withdrawal is more like a storm moving through in waves than a switch that turns off at a set hour. The medication's extended-release design can delay the first wave, followed by a stronger period as opioid effects decline.
The first 12 to 48 hours
During the early window, symptoms may begin gradually. Common signs include:
- Autonomic changes: Sweating, chills, goosebumps, and a runny nose can appear.
- Restlessness: Anxiety, yawning, irritability, and difficulty sitting still may increase.
- Early sleep disruption: Falling asleep or staying asleep can become difficult.
The Psych Central explanation of oxycodone withdrawal notes that extended-release oxycodone withdrawal is often delayed compared with immediate-release oxycodone. The onset may occur around 8 to 24 hours for oxycodone overall, symptoms can peak near 72 hours, and the most intense physical phase often resolves within about 7 to 10 days, although long-acting formulations may extend symptoms to roughly 14 days or more.
Around days 2 and 3
This is often the hardest period. Muscle aches, back pain, nausea, stomach cramps, diarrhea, sweating, insomnia, and flu-like misery can arrive together. Cravings may feel urgent because the brain is seeking relief from both physical discomfort and emotional distress.
The peak doesn't mean the person will feel equally sick every minute. Symptoms can rise and fall, with brief periods of relief followed by another surge. That wave pattern can make the process feel unpredictable even when it follows a broadly recognizable course.
The first week through the second or third week
Physical symptoms usually begin easing after the peak, but improvement is rarely perfectly linear. Energy may remain low, sleep may stay fragmented, and appetite and mood may take time to stabilize.
The American Addiction Centers timeline for opioid withdrawal states that controlled-release opioids such as oxycodone may not produce initial symptoms until up to 36 hours after last use and may continue for 14 days or more. That range explains why a person shouldn't judge recovery by another individual's experience with immediate-release medication.
Why OxyContin Withdrawal Differs From Other Oxycodone
A person may take the last OxyContin dose at night and feel fairly normal the next morning, then develop withdrawal later. The main reason is the formulation. OxyContin is extended-release oxycodone, designed to release medication over time, while immediate-release oxycodone leaves the body more quickly. As opioid exposure falls gradually, symptoms may begin later and remain active longer.
That makes “about a week” an incomplete answer. Someone stopping immediate-release oxycodone may enter withdrawal sooner and improve sooner. Someone stopping OxyContin may not notice the first symptoms right away and may still have acute symptoms during the second or third week.
Short-acting versus extended-release timelines
| Opioid Type | Onset After Last Dose | Peak Symptoms | Typical Duration |
|---|---|---|---|
| Short-acting opioids | 8 to 12 hours | 1 to 3 days | Up to 7 days |
| Extended-release or controlled-release opioids, including OxyContin | Up to 36 hours | Around 72 hours | Up to 14 days or more |
The American Addiction Centers comparison of short-acting and extended-release opioid withdrawal describes this slower pattern for controlled-release opioids, including delayed onset and a potentially longer acute course. A separate oxycodone withdrawal medical summary describes extended-release oxycodone, including OxyContin, as potentially causing withdrawal after at least 12 hours and lasting one to two weeks. Depression and irritability may continue for weeks or months, even after the strongest physical symptoms have eased.
Why individual experiences don't match perfectly
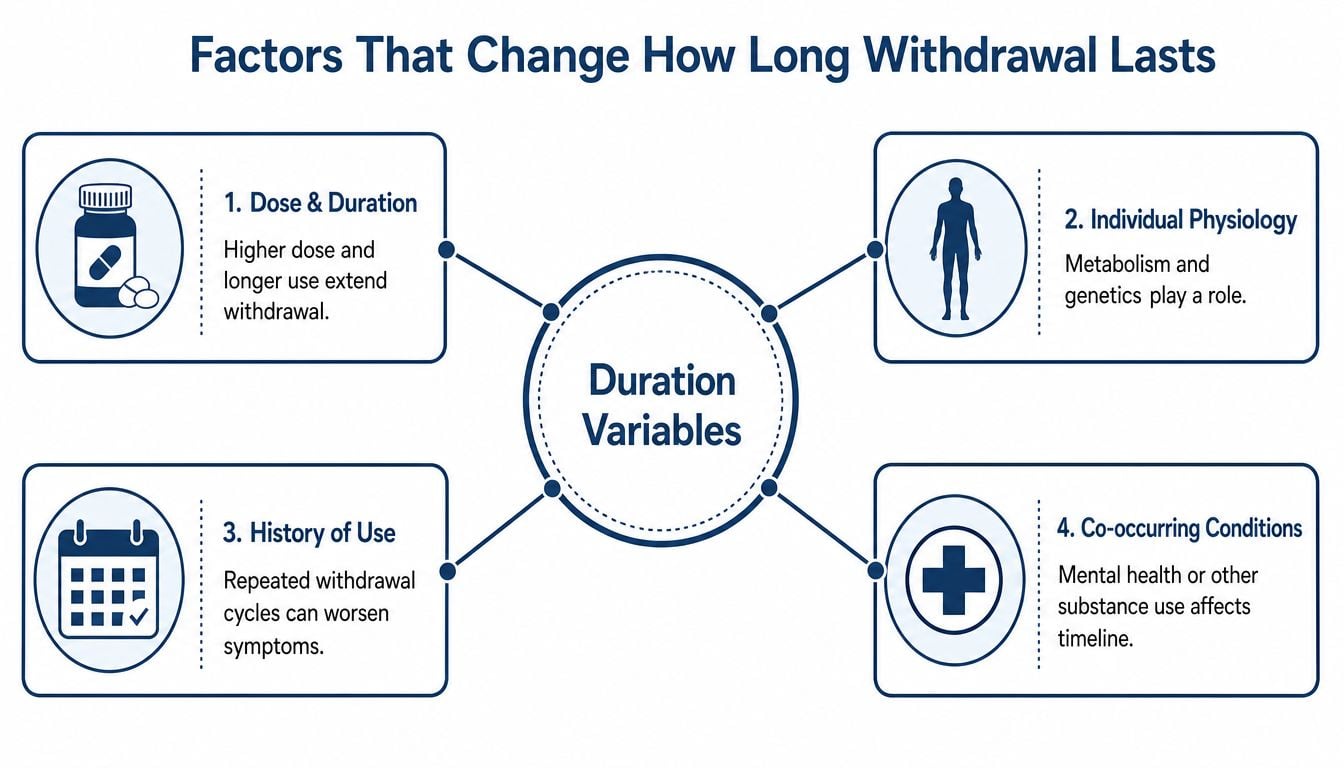
The formulation explains only part of the timeline. Dose, duration of use, metabolism, general health, and other substances can change when symptoms appear and how intense they become. A friend's experience with a short-acting product cannot reliably predict what will happen after stopping extended-release OxyContin.
Acute withdrawal is one window. Cravings, low mood, and sleep disruption can create a longer period of relapse risk, so planning support beyond the first week matters. The practical question is whether the person has medical guidance, monitoring, and a clear treatment path if symptoms become unsafe.
Factors That Change How Long Withdrawal Lasts
Two people can stop OxyContin on the same day and experience different timelines. The medication's formulation matters, but exposure history and personal health help determine how strongly the nervous system reacts after opioid effects decline.
Dose and duration of use
Higher doses and longer use can produce a more difficult adjustment. Someone who used a lower prescribed dose for a limited period may have a different experience from someone who used high doses over years. The clinical discussion of getting off oxycodone emphasizes that formulation, dose, duration, and co-use all influence the acute and protracted course.
The reason for use doesn't eliminate physical dependence. A person taking OxyContin exactly as prescribed for pain can still experience withdrawal after the body adapts to regular exposure. Non-medical use may involve larger or more frequent doses, but the safest response in either situation is individualized medical guidance rather than comparison or judgment.
Health and personal physiology
Metabolism, general health, sleep, nutrition, chronic pain, and mental health can affect how the process feels. Anxiety, depression, trauma symptoms, or untreated pain may become more noticeable once opioid effects no longer suppress distress.
Symptoms also don't always improve in a straight line. A person may sleep better for several nights, then experience another night of severe restlessness or cravings. That fluctuation doesn't necessarily mean the medication is still accumulating or that recovery has failed.
Other substances and medications
Alcohol, benzodiazepines, sedating medications, and other drugs can change the safety picture. Combining substances may increase breathing risk, complicate assessment, or create additional withdrawal syndromes that require separate medical attention. A clinician needs a complete substance and medication history, including substances the person may feel embarrassed to disclose.
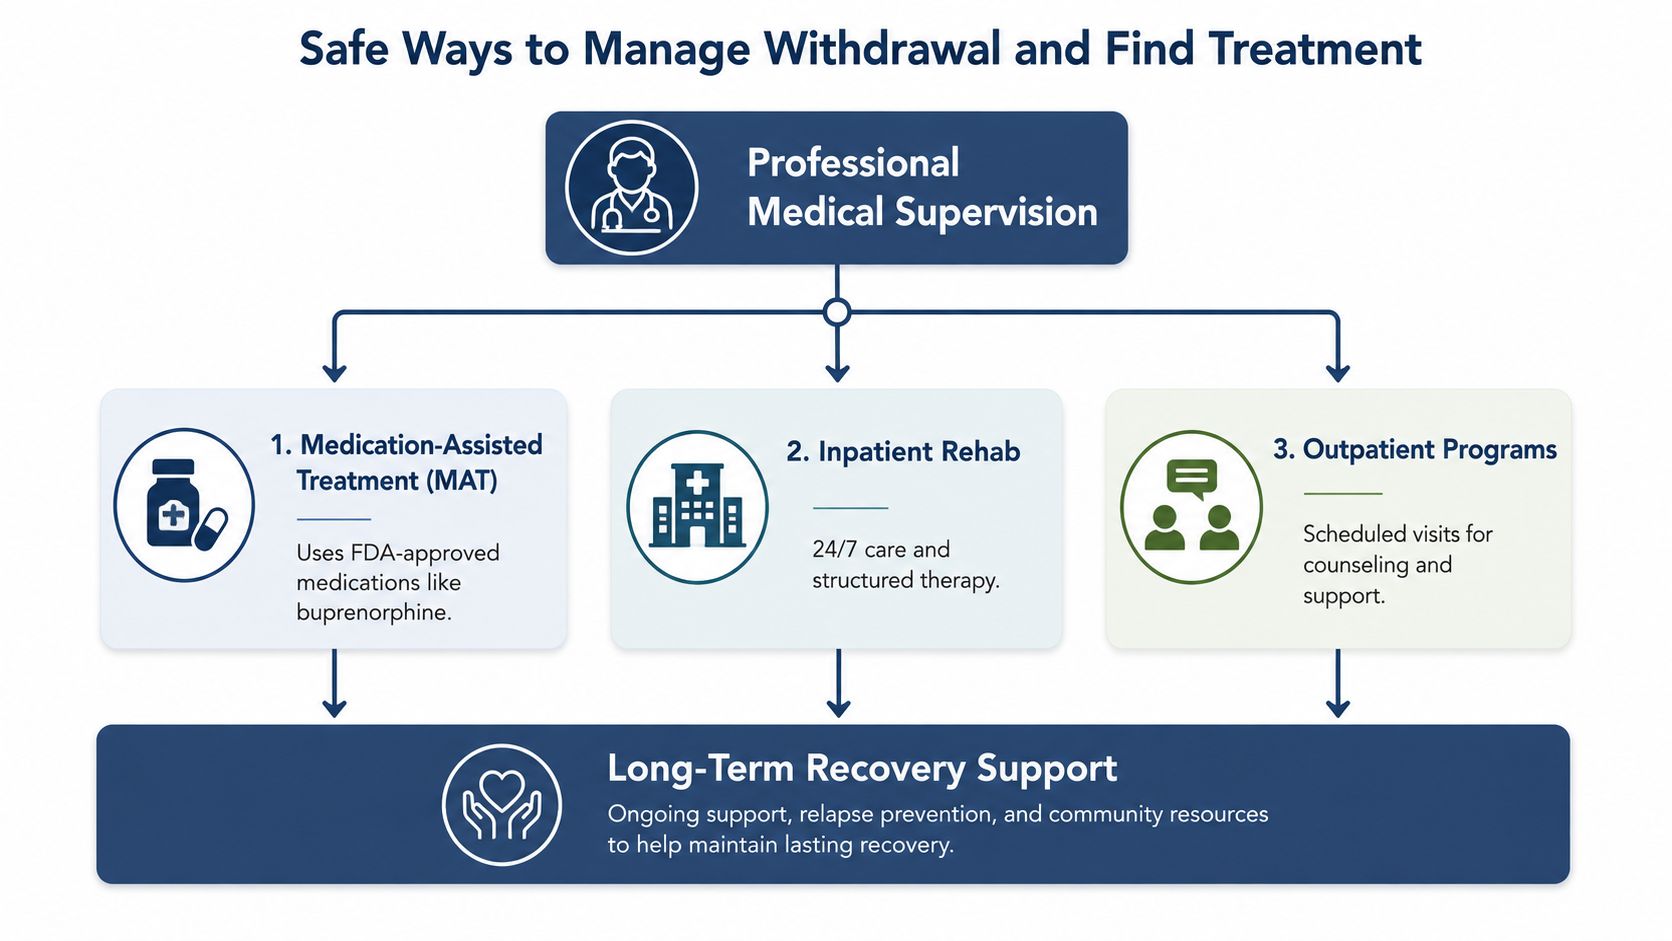
A supervised plan may include a gradual reduction or medication-supported treatment, depending on the person's situation. Guidance about what helps Suboxone withdrawal symptoms can help families understand why medication support should be discussed with a qualified clinician rather than started or stopped without direction.
Acute Withdrawal Versus Post-Acute Withdrawal
A person may wake after several nights of poor sleep, feel emotionally flat, and suddenly face a strong craving just when the worst aches and stomach symptoms have eased. That shift marks an important change in withdrawal. The physical symptoms may be fading while sleep, mood, concentration, and urges to use remain unsettled.
Insomnia, dysphoria, irritability, anxiety, low mood, and cravings may continue for weeks to months. Acute withdrawal is usually intense and body-centered, almost like a severe illness. Post-acute withdrawal is often quieter, but it can linger and interrupt daily life. The two phases overlap for some people, so there is no exact day when one ends and the other begins.
Why the second phase matters
Feeling physically better can create a false sense that recovery is complete. Someone may stop attending appointments, discontinue medication support, or return to familiar settings before having a plan for cravings and emotional distress.
Post-acute symptoms can rise and fall rather than improve steadily. Stress, conflict, pain, poor sleep, and reminders of past use may bring them back. Monitoring helps the treatment team respond when mood, sleep, or cravings change instead of treating a difficult day as a failure.
The key timeline question is not only, “When will the physical symptoms stop?” It is also, “What support will remain when cravings and low mood become the main problem?”
Medication-supported treatment may reduce cravings and help stabilize recovery. Therapy can address emotional and behavioral patterns that opioids may have temporarily covered. Family members can support progress by recognizing lingering symptoms as part of recovery, rather than expecting the person to feel normal as soon as the acute phase ends.

Seek urgent medical help for severe dehydration, chest symptoms, seizures, breathing problems, confusion, or thoughts of self-harm. Withdrawal can often be medically managed, but distress may still lead to relapse, accidental overdose after tolerance changes, or unsafe decisions when someone is alone.
Safe Ways to Manage Withdrawal and Find Treatment
Stopping suddenly without support can expose a person to severe discomfort and intense cravings. Even when opioid withdrawal isn't usually life-threatening by itself, unmanaged symptoms can lead to dehydration, relapse, unsafe mixing of substances, or return to a previous dose after tolerance has fallen.
What supported care can include
A qualified treatment team can assess the OxyContin formulation, dose history, other substances, medical conditions, and mental health needs. The plan may involve medication-supported tapering, treatment for opioid use disorder, symptom management, hydration guidance, sleep support, and close follow-up.
Medication-assisted treatment can be especially important when cravings are strong or previous attempts to stop have ended in relapse. Maintenance treatment shouldn't be treated as a brief detox event that ends as soon as the physical symptoms fade. The World Health Organization guidance on opioid agonist maintenance treatment describes maintenance care as essential health care, reinforcing the need for ongoing treatment when clinically appropriate.
Choosing the right level of care
A person with severe symptoms, unstable housing, serious co-occurring conditions, or unsafe substance combinations may need a more structured setting. Someone who can remain safe at home may benefit from scheduled outpatient visits, therapy, medication management, and reliable family or community support.
Useful treatment components include:
- Medication management: Clinicians monitor withdrawal, cravings, sleep, mood, and medication effects.
- Individual therapy: Sessions can address triggers, trauma, anxiety, depression, pain, and relapse planning.
- Group therapy: Structured groups reduce isolation and create accountability.
- Family therapy: Relatives learn how to support recovery without policing or enabling substance use.
- Cognitive behavioral therapy and mindfulness: These approaches can help a person identify triggers, tolerate distress, and respond to cravings without acting on them.
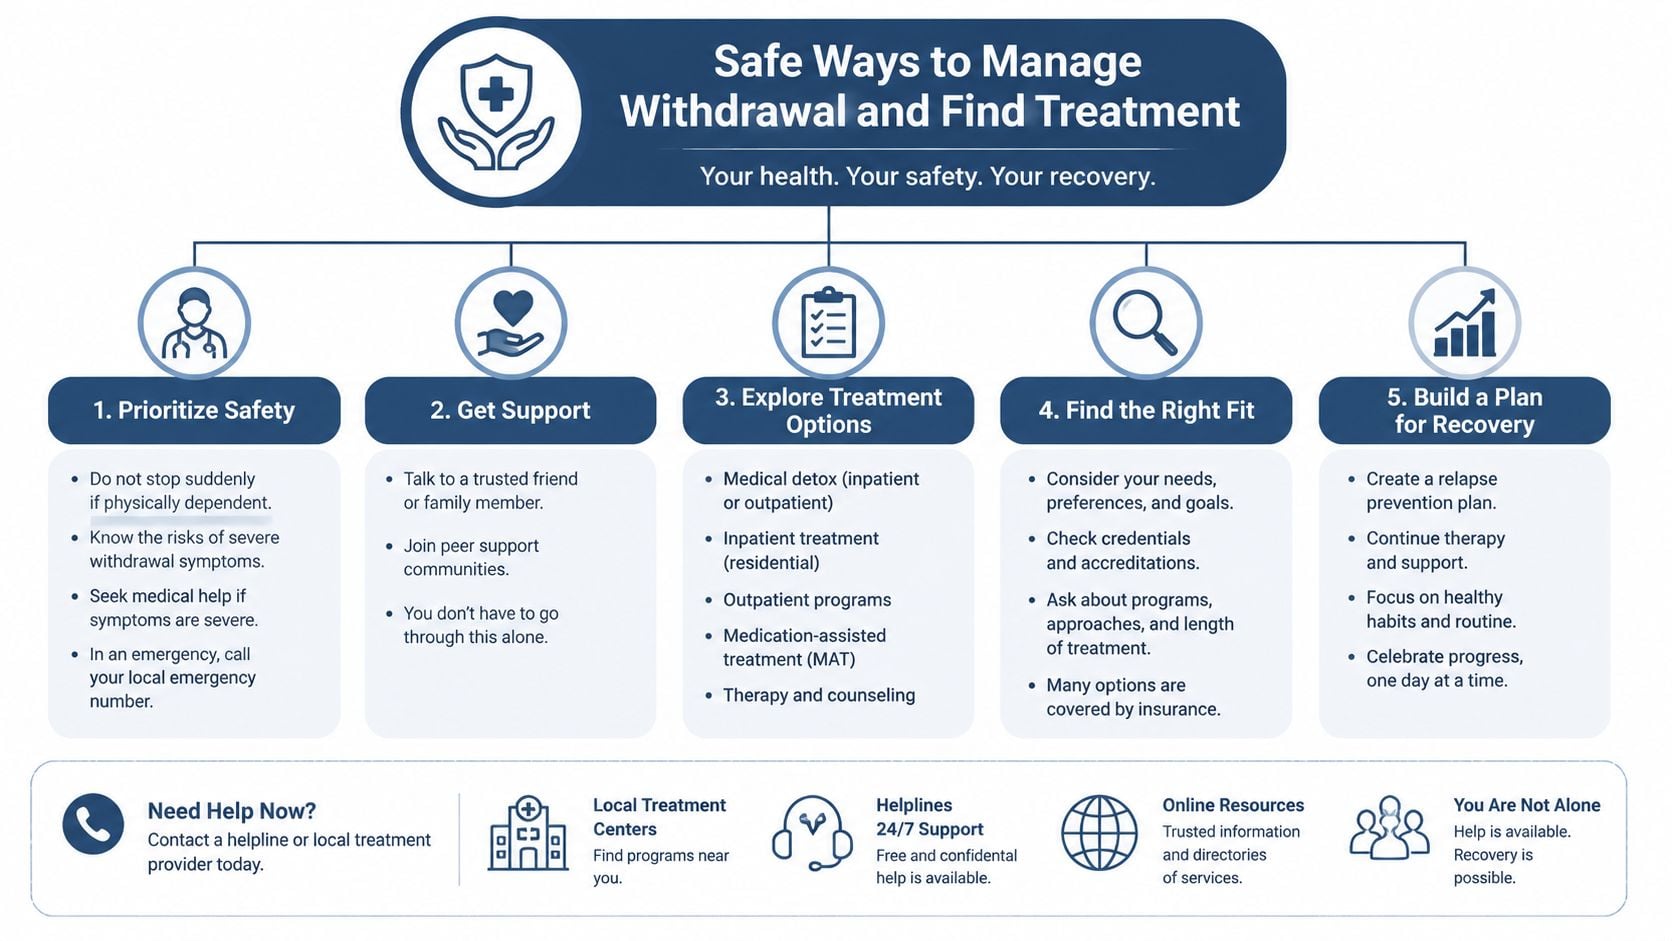
For Massachusetts residents, Cedar Hill Behavioral Health offers a local treatment path through PHP, IOP, and outpatient care, with support matched to symptom severity and independence. The veteran-owned center in Southborough provides same-day admissions, individualized therapy, family involvement, mindfulness, cognitive behavioral therapy, and medication management. Information about detox services in Worcester can help families begin a confidential conversation about appropriate care.
Warning Signs That Need Immediate Medical Care
Withdrawal can involve sweating, aches, nausea, diarrhea, restlessness, and insomnia. Those symptoms can be miserable without automatically indicating an emergency. The danger increases when vomiting or diarrhea causes severe dehydration, when chest or breathing symptoms appear, or when another substance may be involved.
Immediate medical attention is appropriate for:
- Severe dehydration: Confusion, inability to keep fluids down, or little to no urination requires urgent assessment.
- Heart symptoms: Chest pain, fainting, severe weakness, or an irregular heartbeat shouldn't be managed at home.
- Breathing problems: Slow, difficult, or unusual breathing can signal opioid toxicity, especially if substances were combined.
- Seizures: Any seizure requires an emergency call.
- Dangerous thoughts: Suicidal thoughts, plans to self-harm, or thoughts of harming another person require immediate help.

Call 911 or go to an emergency room immediately when any of these red flags appear. A person who may have overdosed should receive emergency care even if withdrawal was expected, because changing opioid tolerance and combining substances can make the situation unpredictable.
For non-emergency treatment planning, Cedar Hill Behavioral Health offers same-day admissions, instant insurance benefits verification, acceptance of most major insurance plans, and payment plans for self-pay clients. Families can also review guidance about relapse and its warning signs while arranging professional support.
The answer to “how long does withdrawal from OxyContin last” is finite but not one-size-fits-all. Physical symptoms commonly occupy the first week and may continue into the second or third week, while sleep, mood, and cravings can require ongoing care. A confidential call to (508) 310-4580 can connect a Massachusetts resident or family member with same-day guidance instead of forcing anyone to manage the hardest days alone.
Cedar Hill Behavioral Health provides same-day admissions and individualized PHP, IOP, and outpatient treatment for people navigating OxyContin withdrawal, cravings, and related mental health concerns in Massachusetts. Visit Cedar Hill Behavioral Health or call (508) 310-4580 to discuss insurance verification, payment options, and the appropriate next step toward supported recovery.








